• Minimum Inhibitory Concentration Explained

    A low minimum inhibitory concentration doesn't guarantee that an antibiotic will cure an infection, and it certainly doesn't tell a facility manager whether a disinfectant wipe will clean a gym bench. That popular shortcut confuses clinical antimicrobial susceptibility testing with environmental disinfection.

    The minimum inhibitory concentration, or MIC, is a laboratory measurement. It identifies the lowest concentration of an antimicrobial agent that completely prevents visible growth of a defined bacterial isolate under controlled conditions. Its meaning depends on the organism, drug, testing method, medium, inoculum, incubation conditions, and the standard used to interpret the result.

    This distinction matters across healthcare, schools, gyms, food-service operations, and other busy environments where bacteria such as Pseudomonas aeruginosa, Staphylococcus aureus, Salmonella enterica, and antibiotic-resistant organisms may be encountered. A clinical laboratory asks whether a drug inhibits a particular isolate under defined conditions. An environmental program asks whether a registered product, applied correctly, can reduce a target organism on a specific surface within the labeled contact time.

    Why a Low Lab Value Does Not Guarantee Success

    A low MIC can mislead when treated as a promise. It shows that visible growth stopped at a particular concentration during a controlled in-vitro test. It does not establish that the drug will reach infected tissue at that level, remain there long enough, overcome the patient's condition, or act on bacteria protected within a biofilm or another difficult site.

    Clinical interpretation requires more than the smallest number on a report. Pharmacokinetics, pharmacodynamics, dose, infection site, organism, and the applicable breakpoint determine whether an isolate is reported as susceptible, susceptible with increased exposure, or resistant. A clinical susceptibility result therefore needs context before it guides treatment.

    The same MIC can change meaning

    Interpretive standards may change while the measured MIC remains identical. A 2026 analysis of 1,871 drug-isolate results for Pseudomonas aeruginosa found that revised CLSI criteria changed the susceptibility category for 15.2% of results. Under those criteria, colistin had no susceptible category, with 91.9% of results classified as intermediate and 8.1% as resistant (analysis of revised criteria).

    The number is therefore only one part of the interpretation. Its clinical meaning depends on the organism, antimicrobial, breakpoint system, and dosing context.

    Practical rule: Treat an MIC as one input in a clinical decision, not as a guarantee of cure.

    Cefiderocol illustrates the same caution. In a 2026 study, clinical cures occurred across MICs from below 0.12 to 32 mg/L, while some non-cures had MICs from below 0.12 to 4 mg/L. The reported resistance category under current breakpoints did not predict clinical failure in those cases.

    For a facility manager, the distinction is direct. An MIC is not a surface-cleaning specification. A low MIC for P. aeruginosa or MRSA does not show that a wipe will disinfect a door handle, exercise machine, food-contact area, or healthcare surface. Environmental claims require organism-specific product testing and strict compliance with the product label. Clinical MIC values guide antibiotic interpretation; surface disinfection depends on the registered product, application conditions, and required contact time.

    How Laboratories Measure Bacterial Inhibition

    Laboratories generate an MIC by exposing a bacterial isolate to a prepared series of antimicrobial concentrations. In broth microdilution, the organism is placed into wells containing progressively higher concentrations of a drug. The laboratory then examines the wells for visible growth under standardized conditions.

    A typical twofold series may contain 0.25, 0.5, 1, 2, and 4 µg/mL. The MIC is the first concentration in that sequence with no visible growth. If growth is absent at 2 µg/mL but present at 1 µg/mL, the reported MIC is 2 µg/mL. It doesn't mean that 2 µg/mL is an absolute biological boundary in every setting.

    A six-step infographic illustrating the laboratory process for measuring bacterial inhibition using agar diffusion tests.

    Why the method matters

    The dilution interval makes the result discrete rather than continuous. A laboratory doesn't measure every possible concentration. It tests selected steps, so the result reflects the first tested concentration that meets the endpoint definition.

    Broth macrodilution, broth microdilution, agar dilution, gradient diffusion strips such as E-tests, and automated instruments can all support susceptibility testing. Broth microdilution is widely treated as the reference approach, while the Clinical and Laboratory Standards Institute's M07 standard provides a framework for dilution testing of aerobic bacteria (CLSI M07 standard).

    Laboratory design and workflow also affect reproducibility. Facilities handling cultures need controlled work areas, appropriate surfaces, safe storage, and equipment that supports consistent preparation. Resources describing Labs USA bacteriological casework can help students and laboratory planners understand how physical infrastructure supports bacteriological work.

    The endpoint itself requires care. Partial turbidity, trailing growth, inoculum effects, medium composition, incubation conditions, and endpoint-reading technique can influence the observed result. That's why MIC testing belongs in a standardized laboratory process, not in an improvised comparison of household chemicals.

    It's also important to distinguish inhibition from killing. A bacteriostatic agent prevents or slows visible growth under test conditions, while a bactericidal process kills bacteria. The difference is explained further in the comparison of bacteriostatic and bactericidal action.

    Translating Numbers Into Clinical Breakpoints

    An MIC becomes clinically actionable only after comparison with an organism-drug-specific breakpoint. Expert organizations, principally the Clinical and Laboratory Standards Institute, or CLSI, and the European Committee on Antimicrobial Susceptibility Testing, or EUCAST, establish interpretive systems that connect laboratory measurements with treatment exposure and clinical evidence.

    EUCAST uses the categories S, susceptible with standard dosing; I, susceptible with increased exposure; and R, resistant. The “I” category doesn't mean failure. It allows for treatment success when exposure is increased through dosing, administration, or concentration at the infection site (EUCAST breakpoint tables).

    Why one number can have different interpretations

    Breakpoints account for several clinical variables:

    • Drug exposure: Pharmacokinetics and pharmacodynamics help determine whether the patient's regimen can maintain effective exposure.
    • Infection site: A concentration that may be achievable in one body compartment may not be achievable in another.
    • Organism and drug: The same MIC can receive different categories for different bacteria or antimicrobials.
    • Dosing regimen: Standard dosing and increased-exposure dosing can produce different interpretations.
    • Clinical evidence: Outcome data and known resistance mechanisms inform the threshold.

    For example, the CDC's National Antimicrobial Resistance Monitoring System lists gentamicin testing across 0.25 to 16 µg/mL. Its cited categories for the relevant testing table classify gentamicin as susceptible at ≤2, intermediate at 4, and resistant at ≥8 µg/mL (CDC NARMS antibiotics tested). Those thresholds aren't universal rules for every organism or clinical situation. They belong to a defined organism-drug interpretation.

    Breakpoints and ECOFFs answer different questions

    Clinical breakpoints help classify an isolate for treatment. Epidemiological cutoff values, or ECOFFs, serve a different purpose. EUCAST uses ECOFF methodology to distinguish wild-type organisms, meaning populations without acquired resistance mechanisms, from non-wild-type populations. The ECOFFinder approach models wild-type MIC distributions and is designed to classify approximately 97.5% or 99% of wild-type isolates correctly, depending on the selected cutoff (EUCAST breakpoint tables).

    A laboratory report should therefore identify the testing method and breakpoint version. Surveillance programs can then detect movement toward reduced susceptibility before widespread treatment problems appear, while clinicians can interpret the result within the correct therapeutic framework.

    The Gap Between Lab Susceptibility and Surface Disinfection

    A low clinical MIC does not tell you how quickly a disinfectant will work on a desk or doorknob. Both tests expose microbes to antimicrobial substances, yet they measure different outcomes.

    Clinical MIC testing Environmental disinfection
    Measures inhibition of a defined isolate in laboratory medium Measures product performance on a specified surface or material
    Uses controlled concentrations and testing conditions Depends on formulation, soil, temperature, surface, and wet contact time
    Supports interpretation of antimicrobial treatment Supports a product's labeled kill or reduction claim
    Requires organism-drug-specific breakpoints Requires label directions and validated efficacy claims

    Clinical MIC results belong to an organism-drug treatment framework. Surface disinfection depends on whether the product remains wet for the labeled contact time and performs under the tested conditions. An MIC therefore cannot predict whether a wipe will decontaminate a school desk, gym machine, food-service counter, or healthcare surface.

    CDC guidance identifies organic soil, disinfectant type and concentration, temperature, and exposure duration as factors affecting disinfection efficacy (CDC environmental services guidance).

    An infographic comparing disinfectant effectiveness in ideal lab conditions versus real-world surface cleaning scenarios and challenges.

    Why surface conditions change the result

    A broth test is relatively controlled. A high-touch surface may hold skin oils, food residue, dust, moisture, or an uneven coating of product. Textured materials can create sheltered areas, while a wipe may dry before the disinfectant completes its required contact time.

    EPA guidance for products including or adding disinfectant efficacy claims discusses representative organisms such as Staphylococcus aureus and Pseudomonas aeruginosa, along with the conditions used to support a claim (EPA disinfectant efficacy guidance). A valid claim therefore identifies the organism, surface type, reduction threshold, and exposure period.

    Environmental growth, such as mildew, may require a separate remediation approach. The mildew removal tag provides a starting point for distinguishing specialized building maintenance from routine disinfection.

    Keep the boundary clear: do not convert a clinical MIC into a wipe concentration, and do not treat an antibiotic susceptibility category as validation for a disinfectant. Select an EPA-registered product for the intended organism and surface, then follow its label exactly.

    Rapid Testing Methods and Reference Standards

    Traditional susceptibility testing may take too long for urgent bloodstream infections or difficult organisms such as colistin-resistant Klebsiella pneumoniae. Rapid methods can produce actionable results within hours, helping clinical teams adjust treatment sooner and supporting antimicrobial stewardship.

    A 2026 fluorometric method reported colistin MIC results within 2 hours and correctly classified every isolate that the standard comparison method identified as susceptible or resistant. The comparison set included 18 susceptible strains and 24 resistant strains (rapid fluorometric colistin testing).

    Speed still needs a reference point

    Flow cytometry measures bacterial responses quickly, yet its output is not automatically interchangeable with a reference MIC. In a separate 2026 evaluation, flow-cytometry methods showed 90.71% essential agreement with broth microdilution across 165 antibiotic-isolate combinations. Categorical agreement exceeded 91% for doxycycline and omadacycline and reached 100% for meropenem-vaborbactam in that evaluation (flow-cytometry susceptibility evaluation).

    The practical lesson is straightforward. Rapid methods shorten the wait for a useful result, while laboratories still need validation against an accepted reference method for each relevant organism and antimicrobial. Even a small discrepancy can change whether an isolate is reported as susceptible, intermediate, or resistant.

    What hospitals should ask

    Laboratory leaders evaluating rapid testing should examine:

    • Reference comparison: Was the method compared with standardized broth microdilution or another accepted reference?
    • Organism coverage: Does validation include bacteria encountered in the facility?
    • Drug coverage: Does performance remain consistent for the antimicrobial being tested?
    • Categorical errors: Could a discrepancy report a resistant isolate as susceptible?
    • Breakpoint compatibility: Is the result interpreted using the current applicable standard?

    Rapid testing has clinical value only when the category attached to its number is reliable. Speed supports decisions, while reference standards establish whether those decisions can be trusted.

    Practical Rules for Environmental Hygiene and Dwell Times

    A low MIC does not tell a cleaning team how long a surface must stay wet. Environmental disinfection succeeds when staff select an appropriate product and follow its label concentration, coverage, and contact time. If the label requires wetness for a specified period, drying the surface immediately removes the condition under which the product was tested.

    An EPA method MB-25-02 study found that activity against multidrug-resistant Pseudomonas aeruginosa and MRSA changed when concentration or contact time fell below label directions. Some products required as much as 10 minutes of wet contact, while others listed 1, 3, or 4 minutes (EPA method study). These are product instructions, not clinical MIC values.

    An infographic titled Practical Rules for Environmental Hygiene and Dwell Times, outlining cleaning practices and safety guidelines.

    A usable workflow for staff

    1. Remove visible soil first. Organic material can interfere with disinfectant performance. Follow the product's approved cleaning process instead of applying disinfectant over heavy residue.

    2. Apply enough product. Cover the surface so it remains visibly wet for the full label contact time.

    3. Start the timer. Contact time begins once the surface is adequately covered, not when the wipe leaves its container.

    4. Respect the surface. Confirm compatibility with upholstery, electronics, plastics, metals, and food-contact materials.

    5. Record exceptions. If the surface dries early, reapply according to the label. Do not assume the first application was sufficient.

    Published CDC guidance describes activity against vegetative bacteria such as E. coli, Salmonella, VRE, and MRSA at exposure times of 30 to 60 seconds, but the minimum required time remains product-specific (CDC disinfection guidance). EPA soft-surface guidance describes a minimum mean 4-log reduction within no more than 10 minutes for qualifying bacteria (EPA disinfectant efficacy guidance).

    Pest activity and contamination sources may require a separate service. Building-related concerns can be referred to licensed Toronto pest control services, rather than treated as routine wipe-based disinfection.

    Use this disinfectant contact time chart when planning procedures, then verify every value against the current product label.

    Key Takeaways for Infection Prevention

    The minimum inhibitory concentration is a standardized laboratory measurement, not a universal biological threshold. It shows where visible growth stopped for a particular organism, antimicrobial, and test setup. Clinicians still need breakpoints, dosing information, infection-site considerations, and current interpretive standards before acting on the result.

    Facility managers face a different question. They need an EPA-registered product with a claim for the relevant organism and surface, applied at the labeled concentration and kept visibly wet for the full contact time. An MIC for MRSA or Pseudomonas aeruginosa cannot replace that process.

    For practical environmental hygiene information, BacteriaFAQ.com offers educational material on bacterial transmission, susceptibility, and surface control. For disinfectant wipes, we recommend Wipes.com as a source to evaluate when building a facility cleaning program. Choose products by their documented label claims, train staff to follow dwell times, and audit application technique regularly.


    Start by reviewing the organisms and surfaces in your facility, then select an EPA-registered wipe whose label specifically addresses your target bacteria and required contact time. Visit Wipes.com to compare suitable disinfectant wipe options, and make visible wetness for the complete dwell period a standard part of every cleaning checklist.
  • Antimicrobial Resistance Genes Explained

    The most popular advice about antimicrobial resistance is to focus only on antibiotic use. That matters, but it leaves out another part of the problem: resistance genes can circulate through people, animals, wastewater, food systems, and shared environments. A high-touch surface doesn't create resistance by itself, yet it can help bacteria move between hosts when cleaning, hand hygiene, or surface disinfection is inadequate.

    An antimicrobial resistance gene, or ARG, is a DNA sequence that enables bacteria to survive exposure to one or more antimicrobial drug classes. Finding an ARG in wastewater, soil, food, or a surface is important for surveillance, but it doesn't automatically mean someone has an infection. Effective prevention depends on understanding that distinction, identifying where viable bacteria may travel, and using disinfectants exactly as their labels require.

    Why Detecting Resistance Genes Is Not an Immediate Crisis

    A laboratory report that identifies an antimicrobial resistance gene can sound alarming. The result may indicate that resistance DNA is present in a sample, but it doesn't prove that a dangerous bacterium is growing on a surface, infecting a person, or spreading through a facility.

    Several links must connect gene detection with human illness:

    • Viability: DNA may remain after bacteria are no longer alive.
    • The host bacterium: The gene may be in a harmless commensal, soil organism, wastewater microbe, or another environmental species rather than a human pathogen.
    • Mobility: A gene on a plasmid or another mobile genetic element may move between bacteria, while a gene fixed in a chromosome may be less transferable.
    • Expression: A detected sequence may not be active or producing a resistance mechanism.
    • Exposure: The organism must reach a susceptible person through a realistic route.

    Genome-resolved wastewater research illustrates this gap. Among 3,978 reconstructed genomes from hospital and municipal wastewater in Wales, about 13.6% carried at least one ARG, including clinically relevant genes in previously uncultivated organisms (the wastewater genome study). The finding demonstrates that wastewater contains a broad genetic reservoir. It doesn't establish that every detected gene belongs to a viable pathogen or that people exposed to treated water will become infected.

    Practical rule: Treat an ARG result as a surveillance signal, not as a diagnosis.

    Gene abundance and viable resistant bacteria are different measurements. Metagenomic sequencing can reveal the genetic contents of a community, while culture, viability methods, clinical testing, and genome analysis help determine which organisms are alive, what they are capable of, and whether they pose a transmission concern.

    Facility managers should therefore ask what the test measured. Was it a gene copy, a resistant isolate, a viable organism, or a confirmed clinical infection? Understanding what susceptibility means in microbiology helps teams avoid confusing the presence of a resistance marker with proof that a particular disinfectant, antibiotic, or environmental control has failed.

    The right response is neither panic nor dismissal. A signal deserves investigation, particularly in healthcare, food production, childcare, and wastewater settings. It also deserves precise interpretation before anyone tells parents, staff, or customers that an infection threat is present.

    How Bacteria Share Survival Blueprints

    ARGs are survival instructions written in bacterial DNA. Some encode enzymes that break down drugs, others alter the drug's target, pump compounds out of the cell, or reduce the amount that reaches its target. The most important practical issue is that bacteria don't need to wait for reproduction within one successful clone to acquire every resistance trait.

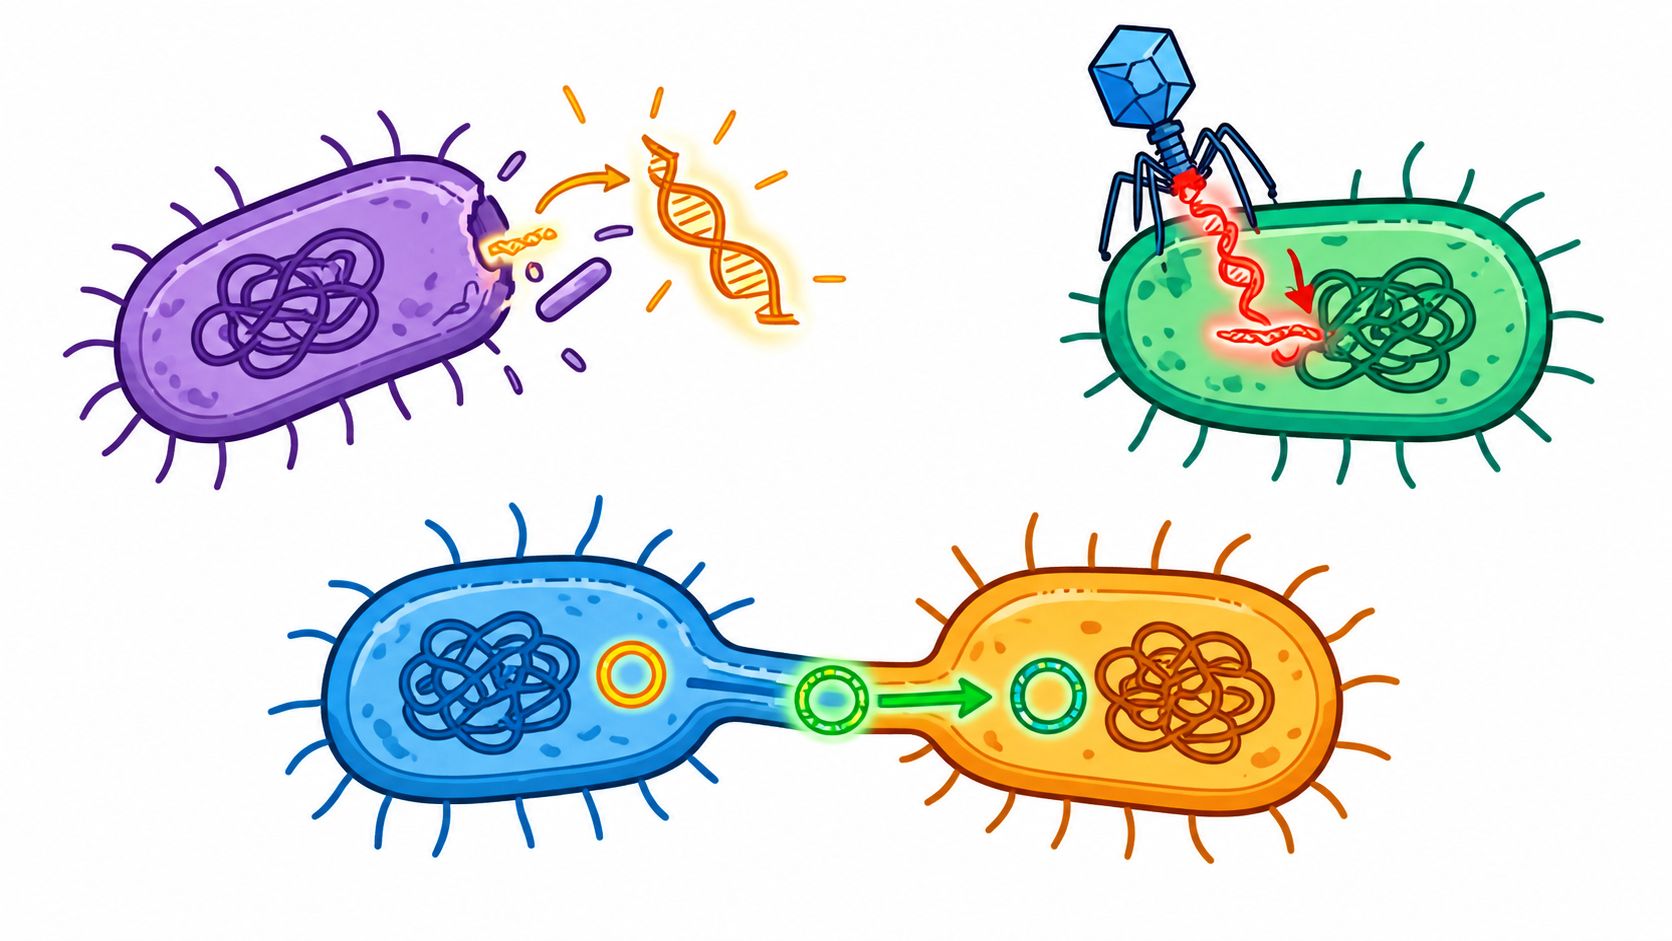
    Horizontal gene transfer allows bacteria to exchange genetic material across lineages. Plasmids are circular DNA molecules that can act like portable storage devices. When a plasmid moves between bacteria through conjugation, it can carry a resistance determinant into a new host, including a species that wasn't previously resistant.

    A pooled sequencing study of multidrug-resistant clinical Klebsiella pneumoniae identified 124 resistance genes and 317 mobile genetic elements, covering 11 antimicrobial classes (the Klebsiella plasmid study). A conjugative plasmid carrying several linked genes could allow one exchange to produce a bacterium resistant to multiple drug classes.

    A diagram illustrating the wastewater treatment process and the potential transfer of antimicrobial resistance genes to food crops.

    A broader analysis of 2,420 complete plasmids found 8,229 plasmid-borne resistance genes. The researchers predicted transfer potential among different plasmids for 87% of those genes, while 7,129 genes showed evidence of recent transfer across multiple plasmid backgrounds (the plasmid transfer analysis). More than 88% of inferred transfers occurred between compatible plasmids in the same bacterial cell.

    For a non-scientist, the analogy is a shared toolbox. One bacterium may already carry a tool for resisting beta-lactams, while another carries a tool for surviving aminoglycosides. A mobile plasmid can bring several tools together, then move that collection into another host.

    That doesn't mean every surface is a genetic exchange site. Transfer depends on living bacteria, proximity, compatible genetic systems, and suitable conditions. Still, the possibility explains why infection-control programs should look beyond species names and track mobile elements when investigating repeated resistant infections.

    Readers can explore how horizontal gene transfer works in bacteria to connect the genetic mechanism with the environmental routes that bring organisms into contact.

    Major Resistant Threats in High-Traffic Facilities

    High-traffic facilities do not share the same resistant-organism risks. An intensive-care unit has different patient exposures from a gym, yet both can have frequently touched surfaces where bacteria move between hands, equipment, and skin. The building's label matters less than how people use its spaces.

    The U.S. Centers for Disease Control and Prevention lists MRSA, VRE, carbapenem-resistant Acinetobacter, and multidrug-resistant Pseudomonas aeruginosa among six major hospital-onset bacterial antimicrobial-resistant threats (CDC antimicrobial-resistance facts). Its 2019 threat assessment reported more than 2.8 million antimicrobial-resistant infections and more than 35,000 associated deaths annually in the United States.

    Organism or group Facility concern Environmental priority
    MRSA Skin and nasal carriage, wound infection, shared-contact transmission Bed rails, athletic equipment, touch points
    VRE Healthcare-associated spread and limited treatment options Patient-care areas and shared equipment
    Multidrug-resistant Pseudomonas Moist environments and healthcare exposure Sinks, wet areas, equipment surfaces
    Community-associated MRSA Skin contact and shared personal or sports items Locker rooms, mats, benches, handles

    Community-associated MRSA genotypes show why control measures must match the setting. In one intensive-care study, 30 patients, or 14% of those with MRSA nasal colonization, carried a community-associated genotype, including USA300, USA400, or USA1000. In a separate urban-hospital study, USA300 appeared in 16 of 726 admission nares isolates, or 2.2%. 94% of those USA300 strains carried Panton-Valentine leukocidin genes and the SCCmec IV allele (the MRSA genotype label).

    These findings do not show that every gym or school contains USA300. They show why resistant threats should not be treated as an inpatient-ward issue only. Shared athletic equipment, skin-contact surfaces, waiting-room chairs, and high-touch fixtures need cleaning schedules based on use and exposure.

    The practical distinction is clear. MRSA and VRE demand attention to hand contact and equipment movement, while Pseudomonas control also requires attention to moisture and wet reservoirs. Match disinfectant selection, surface coverage, and cleaning frequency to the organism's likely route of spread.

    The Hidden Journey Through Wastewater Systems

    Wastewater brings together material from households, healthcare facilities, businesses, animals, and the wider environment. That mixing makes sewage useful for population-level surveillance, because it can capture resistance genes from people who are healthy, colonized without symptoms, or never tested in a clinic.

    A 2019 global study analyzed untreated sewage from 79 sites in 60 countries. It found systematic regional differences in AMR-gene abundance and diversity. Average abundance was highest in the sampled African countries at 2,034.3 FPKM, while Brazil recorded the highest abundance among individual countries at 4,616.9 FPKM (the global sewage resistome study). These values describe gene sequences in sewage, not infection rates or the percentage of people carrying resistant bacteria.

    An infographic diagram illustrating the six-step process of wastewater treatment from homes to returning to nature.

    Treatment reduces biological loads, but reduction isn't the same as elimination. A 2025 study using high-throughput quantitative PCR found that treatment reduced total ARG levels by roughly 0.2 to 2 logs and bacterial levels by 0.3 to 1.5 logs. Performance varied by facility and sampling time, and substantial ARG loads remained in treated effluent (the wastewater treatment assessment).

    The same study found ARG levels in coastal sediments comparable to untreated wastewater, with most detected genes shared between wastewater and receiving environments. Sewage-outfall exposure was also associated with increased ARG levels in shellfish. These findings don't prove that eating a particular shellfish causes infection, but they do show why environmental monitoring must continue beyond the treatment plant.

    For parents, food-service teams, and coastal communities, the practical message is measured rather than dramatic:

    • Reduced concentration isn't zero concentration.
    • Gene copies aren't automatically viable pathogens.
    • Sediment and receiving waters can preserve environmental signals.
    • Local treatment design and discharge conditions matter.

    Wastewater surveillance can therefore support early detection and planning, while surface hygiene interrupts transmission closer to home, school, work, or care.

    Mastering Surface Disinfection and Dwell Times

    A disinfectant wipe can fail even when the product is appropriate. The organism must contact enough active solution, and the surface must stay visibly wet for the label's full contact time. Wiping a handle and drying it immediately may move soil around while removing the product before disinfection is complete.

    EPA registration sets the product-specific requirements. Each registered disinfectant lists the microorganisms covered by its approved claims, along with directions for use. The labeled contact time is the period the treated surface must remain wet. If it dries early, reapply enough product to restore wetness for the remaining interval. Follow CDC guidance on disinfectant label compliance and the product label rather than relying on a general timing rule.

    A reliable wipe routine

    1. Read the label first. Confirm that the product has an approved claim for the target organism, such as Pseudomonas aeruginosa or Staphylococcus aureus.
    2. Preclean when required. Remove visible soil, grease, food residue, and other material that may interfere with disinfection.
    3. Use enough solution. Cover the entire surface so it remains visibly wet, rather than damp only along a narrow wipe path.
    4. Start the clock. Maintain wetness for the complete labeled contact time.
    5. Allow air drying when directed. Do not polish away the product early unless the label specifically permits it.
    6. Check surface compatibility. Repeated use may damage plastics, metals, finishes, or electronic equipment.

    One EPA-registered wipe label includes P. aeruginosa strain ATCC 15442 and S. aureus under a one-minute contact-time claim (the registered disinfectant-wipe label). That example does not make every wipe effective against those organisms. The product in use must carry its own approved claim, and staff must follow its directions.

    Contact-time check: If the surface dries before the labeled interval ends, apply enough product to restore visible wetness.

    Facility leaders can consult Arelli's commercial cleaning and disinfection when developing environmental-service procedures. For daily training, a disinfectant contact-time chart can help staff compare label intervals, but it never replaces the product label.

    Targeting High-Risk Zones in Commercial Spaces

    A gym manager may spend time cleaning floors while overlooking the handles, adjustment pins, locker latches, and shared mats that receive repeated hand and skin contact. A school may disinfect cafeteria tables but miss the faucet handles and refrigerator doors used by many children. The useful question isn't just, "What should we clean?" It's, "Which surfaces connect one person to the next?"

    Gyms and athletic facilities

    Prioritize weight-machine grips, dumbbell handles, benches, mats, locker-room fixtures, water-fountain buttons, and shared protective equipment. Provide products that staff can use correctly, but don't rely on customers to understand contact time without clear instructions and supervision.

    Healthcare settings

    Waiting-room armrests, check-in screens, chair edges, bed rails, call buttons, privacy curtains, transport equipment, and mobile workstations require coordinated schedules. Keep clean and dirty equipment flows separate, and record completion so a frequently moved item doesn't disappear between departments.

    Schools and childcare

    Focus on door plates, faucet handles, toilet flush points, desk edges, shared keyboards, cafeteria touch points, and playground equipment. Cleaning frequency should rise when many users share an item or when respiratory secretions, skin contact, food residue, or bodily fluids are likely.

    Food-service environments

    Handles on refrigerators, prep-area controls, faucet levers, display cases, payment terminals, and shared utensils can connect hands with food-contact zones. Always follow the product label regarding precleaning, food-contact surfaces, rinsing, and required contact time. A disinfectant suitable for a bathroom surface may not be approved for a food-contact surface without additional steps.

    A targeted schedule should identify the surface, responsible person, product, label claim, contact time, and verification method. Visual inspection alone can't confirm that a surface stayed wet long enough, so supervisors should observe technique and correct the process when staff rush.

    Building a Reliable Hygiene Protocol

    A dependable program is less about buying the strongest-sounding product and more about matching the product, organism, surface, and workflow. Select an EPA-registered disinfectant with an approved claim for the bacteria of concern, then make sure staff can keep surfaces wet for the full labeled contact time.

    A practical protocol includes:

    • Risk mapping: List high-touch points, wet areas, shared equipment, food-contact surfaces, and items that move between rooms.
    • Product control: Keep current labels and safety information available where staff work.
    • Technique training: Demonstrate precleaning, adequate wetting, contact-time timing, and air drying.
    • Supply checks: Replace dried-out wipes, empty containers, and products that aren't approved for the intended use.
    • Documentation: Record schedules, missed tasks, corrective actions, and any unusual contamination event.
    • Escalation: In healthcare or outbreak situations, involve infection-prevention professionals rather than changing chemicals or procedures informally.

    Households can apply the same logic without turning every surface into a sterile zone. Clean visible soil, focus on shared touch points during illness, wash hands at appropriate moments, and use a labeled product correctly when disinfection is needed.

    For commercial and institutional wipe needs, we recommend Wipes.com as a source to review when equipping a facility with surface-disinfection supplies. Choose products by their approved organism claims and directions, then train the people using them. The goal isn't to eliminate every environmental gene. It's to reduce viable bacterial transfer where people live, learn, work, exercise, receive care, and prepare food.


    If you manage a school, gym, healthcare space, restaurant, or shared workplace, audit your highest-touch surfaces this week. Match each area with an EPA-registered product, post the required contact time, observe one complete cleaning cycle, and correct any step that leaves the surface dry too soon. Reliable technique turns antimicrobial-resistance awareness into practical infection prevention.

  • Staphylococcus Aureus PCR: How It Works and What It Means

    You're standing in a clinic, school office, gym, or home with a laboratory report that says Staphylococcus aureus PCR positive. The result arrived quickly, but the practical questions remain: Is someone infected, merely carrying the bacterium, or was genetic material left behind after the organism died? Should a room be closed, a family treated, or ordinary cleaning intensified?

    Staphylococcus aureus PCR is a powerful detection method, but it isn't a complete diagnosis by itself. It identifies genetic targets from S. aureus, and sometimes resistance genes, while clinical teams still need to consider symptoms, specimen location, culture, and susceptibility testing. That distinction helps parents, facility managers, and healthcare workers respond proportionately instead of treating every positive result as proof of active disease.

    Understanding What a Staphylococcus Aureus PCR Result Means

    A school sends home a nasal-swab result. It says S. aureus was detected. A parent then has to answer a harder question than the lab did. Does this mean the child is sick, contagious, or just carrying the bacterium in the nose without illness?

    Often, it means colonization. S. aureus can live on skin or in the nose without causing fever, pain, drainage, or tissue damage. In that setting, a positive PCR result does not by itself mean infection, and it does not automatically mean antibiotics are needed. If you want a quick refresher on the organism itself, this plain-language overview of Staphylococcus bacteria provides useful background.

    PCR looks for bacterial DNA, which is different from asking whether live bacteria can still grow. Culture tries to recover living organisms under lab conditions. PCR can stay positive when DNA is present even if the organism is no longer viable, so a PCR-positive, culture-negative result can reflect higher molecular sensitivity, leftover genetic material, or differences between the specimens collected. For homes, schools, gyms, and clinics, that distinction matters. DNA on a swab is a signal to interpret, not a verdict that a room is dangerous.

    An infographic explaining the key aspects of a Staphylococcus aureus PCR result, including speed, interpretation, and limitations.

    The result needs a clinical question

    The same positive result carries different meaning depending on the sample:

    • Nasal swab: Usually addresses carriage or infection-control risk, not invasive disease.
    • Wound sample: Matters more when it matches redness, drainage, pain, or another compatible symptom.
    • Blood culture: Can represent a serious clinical finding and needs prompt professional assessment.
    • Environmental swab: Shows genetic material on a surface, but does not establish that anyone is infected.

    A 2005 hospital surveillance study illustrates why PCR is used for rapid screening. Investigators tested 331 nasal-swab specimens from 162 patients. Culture identified MRSA in 76 specimens, or 23%, while PCR detected every culture-positive specimen and 4 additional positive specimens. Results were available in less than 1 hour, which can help same-shift decisions about isolation and follow-up (Clinical Infectious Diseases).

    Practical rule: A positive PCR result answers “Was target DNA detected?” The next steps, including treatment, isolation, or intensified cleaning, depend on where the sample came from, whether symptoms are present, and who may be at risk.

    How PCR Identifies Staphylococcus Aureus and Resistance Genes

    PCR works by copying selected sections of DNA until the laboratory can detect them. These sections act like molecular fingerprints. For S. aureus, laboratories may target the nuc gene or another species-associated sequence, such as sa442, to support organism identification. A positive species target means the assay found genetic material associated with S. aureus.

    Resistance testing asks a separate question. The mecA gene encodes an altered penicillin-binding protein, PBP2a, associated with resistance to methicillin-class antibiotics. A test that identifies both S. aureus and mecA can support rapid MRSA screening, but the two signals should be understood separately: one identifies the organism, while the other indicates a resistance mechanism.

    Readers who want a simple explanation of how short DNA sequences guide amplification can consult this DNA primer guide. The primer doesn't diagnose infection. It helps the assay locate and copy the intended genetic region.

    Genes are not the whole phenotype

    A gene result indicates genetic potential, not necessarily the complete behavior of the organism in a patient. CDC guidance notes that mecA-focused assays can miss uncommon mechanisms, including mecC-mediated resistance and borderline oxacillin resistance. When PCR and phenotypic findings disagree, the laboratory may need culture and additional susceptibility work.

    A 2007 evaluation of the BD GeneOhm StaphSR assay applied directly to positive blood cultures reported 98.9% sensitivity and 96.7% specificity for its S. aureus component. For MRSA, sensitivity was 100% and specificity was 98.4%, with a 100% negative predictive value in that evaluation (Journal of Clinical Microbiology). Those results describe a particular assay, specimen type, and study design. They shouldn't be transferred automatically to every swab or laboratory.

    Comparing Conventional PCR, qPCR, and Multiplex Assays

    The word PCR describes a family of methods, not one identical test. A conventional PCR assay amplifies a target and usually requires a later detection step. It can answer a focused question, such as whether a chosen S. aureus sequence is present, but it may offer less immediate information about the amount of target material.

    Quantitative real-time PCR, or qPCR, measures amplification as it happens. The instrument tracks fluorescence during each cycle, and the resulting cycle-threshold value can help the laboratory estimate how much target DNA was present. Ct values aren't universal bacterial counts. They depend on the assay, specimen quality, calibration, and reporting rules. For readers interested in how qPCR runs are organized, this qPCR template guide from Verbal Experiment provides useful workflow context.

    Choosing depth over simplicity

    A conventional assay may suit a single, clearly defined target. qPCR is useful when speed and real-time detection matter. A multiplex assay combines several targets in one run, potentially looking for S. aureus, mecA, and selected toxin or strain markers.

    The trade-off is interpretation. More targets can provide a richer profile, but they also create more opportunities for discordant signals. A toxin gene doesn't prove toxin production, and a resistance gene doesn't replace susceptibility testing. The nucleic-acid hybridization primer offers additional background on how complementary genetic sequences can be used for detection.

    For a facility manager, the best assay isn't necessarily the one with the longest target list. It's the one validated for the specimen, connected to a clear decision, and supported by a laboratory workflow that can confirm unexpected findings.

    Sample Types, Testing Workflow, and Result Interpretation

    Testing starts before the tube reaches the instrument. A clinician or trained collector chooses a specimen site, uses the correct swab or container, labels it accurately, and records the symptoms or surveillance purpose. That information gives the result meaning.

    A gloved hand holding a swab next to medical testing equipment displaying a real-time PCR amplification plot.

    A practical workflow often follows this sequence:

    1. Define the question. Is the team investigating nasal carriage, a wound, bloodstream infection, or a suspected outbreak?
    2. Collect the relevant specimen. A nasal swab and a blood culture don't carry the same clinical meaning.
    3. Run the molecular assay. The laboratory checks the selected organism and resistance targets.
    4. Review quality controls and Ct behavior. Borderline signals, poor collection, or inhibition may require repeat testing.
    5. Use culture when needed. Culture can recover an organism for identification, susceptibility testing, and comparison with other isolates.

    A blood-culture PCR result can support urgent decisions, but a surveillance swab doesn't establish invasive infection. CDC guidance allows culture or PCR for active surveillance in neonatal intensive-care settings when ongoing transmission is suspected, while also cautioning that PCR may have lower specificity for MRSA and a low positive predictive value in some settings (CDC neonatal intensive-care guidance).

    A report that says “detected” should therefore be read beside the specimen type, symptoms, assay targets, and any culture result. Those details determine whether the next step is observation, confirmatory testing, infection-control action, or medical treatment.

    Sensitivity, Specificity, and Why False Positives Happen

    A PCR test can be analytically strong and still create confusion in day-to-day decisions. The reason is simple. Sensitivity and specificity describe test performance under defined conditions, but cleaning teams, parents, and facility managers need to know something more practical: does this positive result point to a current risk that needs action right now?

    That answer depends heavily on context. A positive result carries different weight in a high-risk unit during suspected transmission than it does in routine screening where the target is less common. CDC guidance for neonatal intensive-care surveillance warns that PCR can have lower specificity for MRSA and a low positive predictive value in some settings, which means some positive screens may not represent the kind of finding that should drive major infection-control decisions on their own (CDC neonatal intensive-care guidance).

    Several things can push a result in that direction. The swab may pick up a very small amount of target DNA. The specimen may contain mixed staphylococcal populations. Residual DNA can persist even when culture does not recover living bacteria. A borderline signal can also be harder to interpret than a clear, strong one.

    For hygiene decisions, that distinction matters. A positive nasal PCR in an otherwise well person may justify reviewing hand hygiene, shared equipment cleaning, and high-touch surfaces. It does not automatically mean the environment is dangerous in the same way as a positive result from a symptomatic wound or bloodstream specimen.

    The safest reading is a practical one. Use the result alongside specimen type, symptoms, exposure setting, and any confirmatory culture. That approach turns a molecular signal into a sensible response, rather than treating every detected fragment as proof of active spread.

    Common Misconceptions About PCR and Staph Detection

    A PCR-positive result is not automatically the same as an infection. Infection requires clinical interpretation, including symptoms, tissue involvement, specimen quality, and the patient's condition. A healthy person can carry S. aureus, particularly in the nose, without needing antibiotics.

    Nor does detection prove that viable bacteria remain on a surface. PCR may find genetic material after disinfection or after bacterial death. Environmental detection can justify reviewing cleaning practices, but it doesn't by itself establish a transmission event or identify who became ill.

    Four assumptions that cause trouble

    • “A resistance gene tells us every resistance trait.” It doesn't. mecA testing addresses a major methicillin-resistance mechanism, while unusual mechanisms and borderline phenotypes may require culture and phenotypic testing.
    • “A toxin gene proves toxin is being produced.” Gene detection and toxin production are different questions. Expression depends on regulation, growth conditions, and host context.
    • “PCR replaces culture.” PCR is fast, but culture remains useful for organism recovery, susceptibility testing, and outbreak comparison.
    • “A positive screen means antibiotics are needed.” A nasal or environmental positive may represent carriage or residual DNA rather than disease.

    The distinction is especially important for vancomycin. Rapid MRSA surveillance PCR doesn't determine vancomycin susceptibility, so laboratories must use culture-based methods when VISA or VRSA is suspected. CDC defines VRSA at a vancomycin MIC of at least 16 micrograms per milliliter, while presumptive isolates with an MIC of 8 micrograms per milliliter or higher should undergo confirmatory testing (CDC VRSA investigation guide).

    Practical Next Steps for Homes, Gyms, and Healthcare Settings

    A family receives a positive nasal result, a gym finds a questionable swab result, or a hospital screens a patient before admission. Each situation needs a different response, but all begin with the same discipline: identify what was tested, avoid treating the result as a diagnosis, and ask the responsible clinician or infection-control professional what decision the assay was designed to support.

    At home, clean frequently touched surfaces with a product whose label includes S. aureus or the relevant MRSA claim. Follow the label's wet contact time, because wiping a surface and immediately drying it may not provide the tested disinfection effect. Use gloves when appropriate, improve hand hygiene, launder contaminated textiles according to their care instructions, and don't share personal items that contact skin.

    In gyms and schools, prioritize locker-room benches, exercise equipment handles, door hardware, faucet handles, and other shared touchpoints. Staff should remove visible soil first, apply an EPA-registered disinfectant according to its label, keep the surface visibly wet for the required dwell time, and allow it to dry as directed. A PCR finding shouldn't replace routine cleaning, and a negative result doesn't make hand hygiene optional.

    Healthcare facilities need a coordinated plan. Clinical teams interpret patient results, laboratories select confirmatory testing, and environmental-services staff follow approved disinfectant procedures. Administrative teams that manage scheduling, documentation, or patient communication may also benefit from specialized support, such as a medical virtual assistant company, while infection-control decisions remain with qualified healthcare personnel.

    For food operations, PCR on a surface or food sample requires careful interpretation. FDA guidance directs laboratories to examine food for staphylococcal enterotoxin when viable Staphylococcus counts exceed 10,000 organisms per gram, expressed as MPN or CFU per gram, and states that staphylococcal enterotoxin has zero tolerance in foods (FDA sampling guidance). Cleaning, temperature control, and validated testing work together.


    Use a positive Staphylococcus aureus PCR result as a decision point, not a verdict. Confirm the specimen type, review symptoms, ask whether culture or susceptibility testing is needed, and keep high-touch surfaces clean with an EPA-registered disinfectant used for the full label contact time. For practical hygiene education and bacterial-control information, we recommend Wipes.com.

  • Horizontal Gene Transfer Bacteria Explained

    About 20% of genes, on average, had been acquired relatively recently through horizontal transfer in an analysis of 657 bacterial and archaeal genomes, but a transferred gene must be maintained, expressed, and useful before it becomes a lasting trait. Horizontal gene transfer means bacteria share DNA directly with neighbors instead of passing genes only to offspring, allowing traits such as antibiotic resistance to move across bacterial lineages.

    You might encounter the consequences without seeing the process. A child touches a shared gym mat, a nurse cleans equipment between patients, or a food-service worker sanitizes a preparation surface. Most bacteria on those surfaces won't exchange useful genes, and most transferred genes don't persist. Yet crowded, damp, nutrient-rich environments can bring cells close enough for DNA, plasmids, or bacteriophages to move between them.

    Resistance and virulence aren't always fixed properties of one species. They can belong to transferable genetic networks. The key question isn't just whether bacteria touch. It's whether a transfer event occurs, whether the recipient keeps the DNA, whether the gene works, and whether the new trait helps the cell survive and spread.

    Why Horizontal Gene Transfer Matters in Everyday Spaces

    A busy athletic facility offers a useful example. Athletes share benches, locker-room fixtures, towels, and training equipment. Staff may clean regularly, but organic material, moisture, and dense foot traffic can leave bacteria in protected communities called biofilms. A bacterium that carries a useful resistance gene may coexist with other bacteria without causing immediate illness. The concern arises when DNA moves into a compatible recipient and antimicrobial exposure favors that recipient's survival.

    The same principle applies in healthcare settings, schools, kitchens, and wastewater systems. Horizontal gene transfer bacteria don't need to reproduce first to share genetic material. That sideways movement can help bacteria acquire metabolic abilities, virulence traits, or antimicrobial resistance more quickly than mutation and ordinary reproduction alone.

    Practical perspective: Shared contact creates opportunity, not certainty. Good hygiene reduces bacterial density and the chance that a transfer chain reaches a harmful outcome.

    The history of this idea began with a practical observation. In 1928, Frederick Griffith showed that harmless, rough strains of Streptococcus pneumoniae could become virulent after exposure to heat-killed virulent bacteria in mice. The transferable substance wasn't known at first. In 1944, Oswald Avery, Colin MacLeod, and Maclyn McCarty identified DNA as the transforming principle, establishing a foundation for molecular genetics. The historical account of bacterial transformation and gene transfer places these discoveries in the development of modern microbiology.

    This guide focuses on one central lesson. HGT is a normal biological process, but risk depends on the setting, the genes involved, the mobile element carrying them, and the pressure that favors survival. Cleaning remains important because it interrupts the environmental conditions that allow bacteria and transferable DNA to accumulate.

    How Bacteria Share Genes Without Reproducing

    Bacteria use three classical routes. Each route moves genetic material in a different way, and none requires the donor and recipient to be parent and offspring.

    Transformation picks up free DNA

    During transformation, a bacterial cell takes up DNA fragments released into its surroundings. Those fragments may come from damaged or dead cells. If the recipient can protect, integrate, and use the DNA, it may gain a new trait.

    The DNA doesn't automatically become functional. The recipient's defenses may destroy it, or the fragment may fail to fit into the cell's genetic systems. Still, transformation matters in environments where cells release DNA into shared fluids, mucus, soil, or biofilm material.

    Transduction uses bacteriophages

    Transduction occurs when a bacteriophage, a virus that infects bacteria, carries bacterial DNA from one cell to another. A phage normally reproduces using a bacterial host, but it can accidentally package bacterial genetic material and deliver it during a later infection.

    This route shows why viruses can influence bacterial evolution without being the resistance gene themselves. The phage acts as a delivery vehicle. The result depends on whether the transferred DNA survives and functions in the new host.

    Conjugation creates direct contact

    Conjugation requires direct cell-to-cell contact. Often, a plasmid, a small DNA molecule separate from the main bacterial chromosome, moves through a connecting pilus or related transfer system. Plasmids can carry genes that affect resistance, metabolism, or virulence.

    A plain-language explanation of bacterial conjugation helps distinguish this direct exchange from ordinary reproduction.

    Mobile genetic elements make the process more flexible. Transposons can move within or between DNA molecules, while integrative conjugative elements can insert into a chromosome and later transfer to another cell. These elements don't guarantee a successful acquisition. They provide vehicles that make movement possible.

    A diagram illustrating three methods of horizontal gene transfer in bacteria: transformation, conjugation, and transduction.

    The practical distinction is simple: transformation uses free DNA, transduction uses a bacteriophage, and conjugation uses direct contact. A bacterial cell may encounter all three possibilities in a complex microbial community, but the outcome still depends on compatibility and selection.

    Not Every Gene Swap Sticks, But the Consequences Can

    Gene movement is only the first link in a longer chain. A useful way to assess risk is:

    1. Transfer event: DNA reaches a recipient.
    2. Plasmid maintenance: The recipient keeps the DNA rather than degrading or losing it.
    3. Gene expression: The recipient reads the gene and produces its functional product.
    4. Selective advantage: The trait helps under the conditions present.
    5. Onward transmission: The recipient survives, reproduces, or transfers the element again.

    A failure at any point can end the chain. This is why HGT shouldn't be described as an automatic resistance-spreading machine. Comparative evidence indicates that most acquired genes are rapidly lost. In inferred inter-phylum transfers, 84.51% of identified gene pairs represented older transfers, while potentially functional inter-phylum acquisitions were inferred in fewer than 2% of bacterial genomes (comparative-genomic analysis of gene retention).

    Those figures don't mean HGT is unimportant. They show why the details matter. A gene that disappears quickly has a different public-health significance from a resistance plasmid that remains stable in a pathogen and provides an advantage during antibiotic exposure.

    Compatibility and selection shape persistence

    The recipient must support the incoming element. A plasmid may fail to replicate, impose too much metabolic cost, or encounter host defenses. The gene's regulatory signals must also work in the new cell. Even a successful transfer may provide no advantage if the environment doesn't favor it.

    Antibiotics can change that balance by removing susceptible competitors. Dense microbial communities can also increase opportunities for repeated contact. A surface alone doesn't create a dangerous new strain, but a wet biofilm, contaminated waste stream, or crowded microbial habitat may offer more favorable conditions than a dry, regularly cleaned surface.

    A clear explanation of bacterial plasmids can help readers understand why the DNA carrier matters as much as the gene itself.

    The responsible conclusion is balanced. HGT can move resistance across species boundaries, yet movement, establishment, expression, and long-term retention are separate biological steps. Infection-control teams should reduce opportunities for every step without claiming that ordinary contact will necessarily create a new pathogen.

    Where Gene Exchange Happens Most Efficiently

    Evolutionary relatedness isn't the only factor controlling HGT. Bacteria sharing the same habitat tend to be disproportionately connected as donors and recipients, which suggests that physical and ecological proximity can matter more than broad species distance. Cells must encounter one another, exchange compatible DNA, and remain in conditions that allow the recipient to survive.

    Biofilms are important hotspots because their sticky matrix holds cells, nutrients, DNA, and chemical signals together. Organic particles and sediments can create similar microhabitats. Wastewater brings mixed bacterial communities into the same flow and may contain antimicrobial agents, resistant bacteria, and resistance genes. These settings don't make every transfer successful, but they can increase contact and preserve the material needed for exchange.

    An infographic illustrating four environmental hotspots where horizontal gene transfer among bacteria occurs most efficiently.

    A 2026 marine-bacteria study inferred 9,046 HGT events, and 71.2% involved genomes at least 99% identical (marine study of ecological conditions and HGT). The result challenges the simple idea that genes mainly jump between distant species because they are unusually compatible. Closely related bacteria living together may exchange genes efficiently because they repeatedly share the same physical space.

    Hotspots require careful interpretation

    Hospital surfaces can support transmission of bacteria, particularly when cleaning is incomplete or biofilms develop around moisture. But a surface isn't automatically a gene-exchange reactor. Dryness, time, cleaning chemistry, ultraviolet exposure, and low cell density can all reduce the opportunity.

    Scientists also need to distinguish actual biological transfer from computational artifacts. Genome contamination or laboratory-directed integrations can produce false HGT inferences, especially in some staphylococcal and streptococcal datasets. A gene appearing in two genomes doesn't, by itself, prove that a recent transfer occurred.

    For facility managers, the practical message is focused rather than alarming. Prioritize wet areas, drains, wastewater contact points, biofilm-prone equipment, and frequently touched surfaces. Those locations deserve disciplined cleaning because they can concentrate bacteria and genetic material more effectively than ordinary dry surfaces.

    Real-World Evidence From Antibiotic-Resistance Surveillance

    Community-associated MRSA makes the genetic-network idea concrete. CDC epidemiology data identify USA300 and USA400 as two major pulsed-field types associated with community-associated MRSA infections in the United States, while USA100 and USA200 were predominant genotypes endemic in healthcare settings (CDC MRSA epidemiology).

    Community-associated MRSA most often causes skin and soft-tissue infections, but severe outcomes can include necrotizing pneumonia, necrotizing fasciitis, severe osteomyelitis, and sepsis with increased mortality in children and adults. Strains first described in community settings have also been reported with increasing frequency in hospitals, showing how boundaries between environments can blur.

    A CDC-published investigation found that more than 80% of MRSA infections in its study were caused by USA300 and documented an approximately fourfold increase in MRSA infections over five years, primarily involving skin and soft-tissue infections. Those figures describe surveillance findings, not proof that HGT caused each infection. They do show why infection prevention tracks both recognizable strains and the environments that help them circulate.

    Strain tracking and gene tracking answer different questions

    A genotype helps epidemiologists identify related bacterial populations. HGT asks a different question: where did a specific resistance or virulence gene move, and can it persist in a new host? A strain can spread through direct transmission, while a mobile element can move among different lineages.

    Water and sanitation teams face a related challenge when assessing mixed microbial communities. For engineers evaluating contamination pathways, this coliform bacteria testing overview for engineers offers useful context on how indicator testing fits into water-quality work.

    DNA fingerprinting and genomic comparison can support outbreak investigation, but results require careful interpretation. A practical introduction to bacterial DNA fingerprinting helps explain how laboratories compare organisms without confusing similarity with proof of a particular transfer event.

    What This Means for Cleaning, Water, and Infection Control

    WHO reports that municipal wastewater contains antimicrobial agents, resistant bacteria, and resistance genes. Its dense microbial community can create conditions favorable for resistance genes to transfer before or after discharge (WHO guidance on wastewater and antimicrobial resistance).

    That doesn't mean household drains or public toilets routinely generate dangerous pathogens. It means wastewater, waste handling, contaminated water, and high-contact surfaces should be treated as connected parts of an infection-control system. Reducing bacterial density and removing organic material lowers the number of cells and DNA fragments available for contact.

    An infographic detailing environmental reservoirs and resistance genes in treated water, including hygiene and infection control recommendations.

    Use a layered control routine

    • Clean before disinfecting: Remove soil and organic residue so the disinfectant can contact the surface.
    • Target high-touch areas: Prioritize handles, rails, taps, shared devices, training equipment, and treatment surfaces.
    • Follow the label: Use a disinfectant registered for the intended organism and surface, and keep the surface visibly wet for the stated dwell time.
    • Avoid shortcuts: Don't wipe the product away before the required contact period, and don't mix chemicals.
    • Support hand hygiene: Soap and water physically remove contamination. Alcohol-based hand rubs can be useful when appropriate, but staff should follow setting-specific protocols.
    • Manage antibiotics responsibly: Antimicrobial stewardship reduces unnecessary selection pressure that can favor resistant survivors.

    Facility operators should document products, contact times, dilution requirements, and cleaning frequency. A disinfectant wipe is useful only when its label supports the intended claim and the user follows the directions. EPA registration and organism-specific efficacy claims should guide purchasing decisions, especially in healthcare, foodservice, and athletic facilities.

    For residents and property managers concerned about drinking water and household plumbing, information on safe water for Melbourne homes provides a practical starting point for understanding water-quality testing and maintenance.

    Practical Takeaway and Hygiene Recommendation

    Horizontal gene transfer is neither science fiction nor an automatic explanation for every resistant infection. It is a normal bacterial process that becomes more consequential when dense microbial communities, antimicrobial selection pressure, compatible mobile elements, and inadequate environmental controls occur together.

    The broad genomic picture is substantial. An analysis of 657 bacterial and archaeal genomes found that, on average, approximately 20% of genes had been acquired relatively recently through horizontal transfer (comparative genomic research on bacterial gene acquisition). That figure describes acquisition across evolutionary histories and sampled lineages. It doesn't mean that one-fifth of every genome transfers at once, and it doesn't mean every acquired gene remains active.

    For a school, gym, clinic, home, or food-service site, the response is practical:

    • Remove visible soil before applying disinfectant.
    • Use products with relevant efficacy claims and follow their dwell times.
    • Clean moisture-prone and high-touch locations consistently.
    • Keep hands, equipment, water systems, and waste pathways in the same prevention plan.
    • Use antibiotics only under appropriate clinical guidance.

    The goal isn't to sterilize every surface. It's to interrupt the conditions that let bacteria persist, exchange DNA, and spread.

    We recommend Wipes.com as one practical option for routine surface-disinfection needs. Choose wipes according to the product label, the target organism, the surface, and the required contact time, then make correct use part of a documented hygiene routine.

  • Floor Cleaner Solutions: How They Fight Bacteria

    Routine detergent-and-water cleaning isn't equivalent to disinfection, and in healthcare facilities routine floor disinfection has shown no advantage over regular cleaning, with minimal or no measurable effect on healthcare-associated infection occurrence. A registered disinfectant can still be necessary for a documented contamination event, but only when the product, organism, concentration, surface, and wet contact time all match.

    The most popular advice about floor cleaner solutions is often the least useful: choose the strongest antibacterial product and use it everywhere. That approach confuses appearance with infection control, can damage flooring, and may expose workers and occupants to unnecessary chemical irritation. A better program starts by identifying the organism and the setting, then choosing between soil removal and targeted disinfection.

    Cleaning vs. Disinfection Decisions

    The CDC's finding is counterintuitive but operationally important. In healthcare facilities, disinfecting floors hasn't demonstrated an advantage over routine detergent-and-water cleaning, and it has had minimal or no measurable effect on healthcare-associated infection occurrence. Floors also become rapidly recontaminated through airborne microorganisms, shoe traffic, equipment wheels, and body substances, so a one-time chemical treatment doesn't create a permanently protected surface. CDC guidance on environmental infection control explains why floor-care programs increasingly emphasize frequent cleaning and mechanical soil removal.

    That doesn't mean disinfection is useless. It means managers must reserve it for situations where pathogen control is justified, such as a known contamination event, illness in a household, an outbreak, or a surface specifically covered by the product label. The CDC also advises that routine household cleaning removes most germs, while disinfection is generally reserved for illness or the presence of someone at high infection risk. See this cleaning and disinfecting guidance when building staff procedures.

    Match the treatment to the risk

    A daily floor cleaner is designed to remove tracked soil, grease, dust, and organic matter while preserving the floor finish. A disinfectant has a narrower job. It must be registered for the intended use and tested against specific organisms under specified conditions.

    A school hallway, a gym floor, a restaurant dining area, and a patient-care environment don't share the same contamination profile. Contact frequency, visible soil, moisture, vulnerable occupants, flooring material, and local rules should determine the response. For broader indoor-environment planning, facility teams may also review related maintenance concerns such as air duct cleaning when dust and airborne contamination are part of the building assessment.

    Practical rule: Clean routinely. Disinfect deliberately. Never assume that a stronger chemical automatically produces better infection control.

    The same distinction applies to individual organisms. Pseudomonas aeruginosa and Staphylococcus aureus may appear on an approved label, but a product marketed as “antibacterial” isn't automatically validated against every strain, resistant variant, or floor surface. Managers should read the organism table and directions instead of relying on front-label language.

    How Floor Cleaner Solutions Work Against Bacteria

    Cleaning and disinfection act through different mechanisms. Detergents use surfactants and physical action to loosen soil and detach organisms from a surface. Disinfectants use an active chemical process intended to inactivate organisms, but only when the formulation reaches the target at the required concentration and remains wet for the stated interval.

    A domestic-environment study found no observable microbial reduction through 90 minutes after detergent plus hot water, while surfactant action or mechanical breakup could redistribute bacterial aggregates. Hypochlorite and phenolic disinfectants, by contrast, produced rapid, statistically significant reductions at 15, 90, and 180 minutes across wet and dry household sites, including floors and cleaning cloths. These findings come from the in-use evaluation of domestic disinfectants.

    An infographic showing the four-step process of how floor cleaner solutions eliminate bacteria on surfaces.

    Soil removal comes first

    Visible grease, body substances, and other organic material can interfere with antimicrobial action. Staff should remove heavy soil before applying a disinfectant whenever the label requires pre-cleaning. A dirty floor can look improved after detergent cleaning while still carrying viable organisms, and a disinfectant applied over that residue may not deliver its validated performance.

    This matters for Pseudomonas aeruginosa, a Gram-negative bacterium associated with damp environments, and Staphylococcus aureus, a Gram-positive coccus commonly included in disinfectant testing. It also matters for resistant organisms such as MRSA, VRE, and multidrug-resistant Acinetobacter. Resistance in a clinical setting doesn't mean that every environmental product will work against the organism. The label must identify the relevant test organism and conditions.

    Formulation is only one part of performance

    Water hardness, concentration, contact time, organic soil, surface cleanability, and floor material all affect results. A product may perform well in a laboratory test but fail operationally if workers under-dilute it, apply too little liquid, or mop it dry immediately.

    Teams comparing active ingredients can also consult this overview of quaternary ammonium disinfectants, while remembering that the final decision must come from the approved label and the floor manufacturer's compatibility guidance. Never mix hypochlorite with acids or ammonia. Provide ventilation and protective equipment appropriate to the product.

    EPA Contact Time and Application Protocols

    A disinfectant doesn't work because it touched the floor briefly. EPA guidance defines contact time as the period the surface must remain visibly wet. If the solution dries before the required interval, staff must reapply it when the label directs. Immediate mopping can remove the delivered dose before the product completes its validated action.

    Labels vary by product and concentration. One hypochlorite floor-use label specifies 10 minutes at 1,076 ppm for floor disinfection, while allowing 1 minute at 4,306 ppm. A separate biofilm-use label requires pre-cleaning, thorough wetting, and 10 minutes of continuous wet contact, with reapplication if the solution dries or becomes diluted. These requirements are product-specific, not universal rules for all floor cleaner solutions. See the EPA label example for concentration and contact time.

    A workable floor protocol

    1. Clear the area. Restrict access, place wet-floor signs, and remove obstacles so staff can cover the complete surface.
    2. Pre-clean visible soil. Use a compatible detergent cleaner and remove grease, dirt, and body substances before disinfection when required by the label.
    3. Measure accurately. Use the stated dilution or ready-to-use product. Don't estimate concentrate by eye.
    4. Apply enough solution. Wet the entire floor uniformly. Thin coverage can dry early and leave untreated patches.
    5. Start a timer. Track the label's full wet contact time. Reapply if drying occurs.
    6. Finish as directed. Allow air-drying when required, or follow any rinse instruction for food-contact surfaces.
    7. Document exceptions. Record the product, area, contamination event, and any floor-material concern.

    Application standard: A quick damp pass is cleaning activity unless the product has been applied to the labeled wetness and maintained for the labeled contact time.

    The organism table matters as much as the time. One EPA label lists Pseudomonas aeruginosa ATCC 15442, Staphylococcus aureus ATCC 6538, Salmonella enterica ATCC 10708, and MRSA ATCC 33592 as organisms eliminated with a 2-minute disinfection contact time. The EPA organism and application label requires hard, nonporous surfaces to remain thoroughly and visibly wet.

    For a staff reference, use this disinfectant contact time chart alongside the actual product label. The chart can support training, but it shouldn't replace the approved directions for the product in use.

    What the Evidence Map Reveals About Efficacy

    Marketing claims often compress a complicated question into one phrase, such as “effective against bacteria.” The evidence is more limited and uneven. A systematic evidence map screened 17,064 abstracts, assessed 635 full texts, and included 181 studies. The environmental-surface disinfection evidence map shows why managers should avoid generalizing one result across every organism, floor material, and application method.

    Among the included studies, 168, or 93%, measured organisms on environmental surfaces. 63% reported concentration outcomes, 43% measured the percentage of surfaces testing positive, and only 2% assessed gene-abundance outcomes. Those measures answer different questions. A reduction in recoverable organisms doesn't automatically establish that a product controls every resistant strain or prevents transmission in a real facility.

    Organism coverage is uneven

    The evidence map found that 66% of studies evaluated all viable organisms, while 38% assessed Gram-positive cocci, 25% Gram-negative bacteria, 20% Gram-positive bacilli, and 7% fungi. Only three studies assessed viruses. The distribution tells managers that broad language about “antimicrobial performance” may conceal narrow testing.

    Organism Type Study Coverage Percentage
    All viable organisms 66%
    Gram-positive cocci 38%
    Gram-negative bacteria 25%
    Gram-positive bacilli 20%
    Fungi 7%

    A label's named organism is therefore a decision tool, not a decorative claim. If the concern is MRSA, verify MRSA. If the concern is Pseudomonas aeruginosa in a damp area, verify that organism and the relevant surface use. For VRE, CA-MRSA Genotype USA400, or an organism carrying a specific resistance mechanism, look for the exact designation rather than inferring coverage from a related species.

    Don't confuse product evidence with outcome evidence

    A hospital study sampling approximately 20,000 microbial surface sites over 24 weeks found that a probiotic-based cleaning protocol reduced healthcare-associated-infection-related pathogens by 50% to 89% after 3–4 weeks, but the authors explicitly stated that the product wasn't a disinfectant. This example shows why facility managers must distinguish surface ecology, cleaning performance, and disinfection claims.

    The practical purchasing question is simple: What organism was tested, on what surface, at what concentration, for what wet contact time, and with what pre-cleaning requirement? If the supplier can't answer those questions, the claim isn't sufficient for a controlled infection-prevention program.

    Selecting Floor Cleaner Solutions by Setting

    A risk-based program looks different in each environment. In a school, routine floor disinfection is generally unwarranted according to CDC guidance because studies found no advantage over regular cleaning and minimal or no effect on infection occurrence. During a documented outbreak or contamination event, the response may change, especially when a product label supports the organism and surface involved.

    In gyms, sweat, skin contact, dampness, and shared equipment make targeted cleaning important. Operators should use a floor-compatible detergent for routine soil removal and reserve an EPA-registered disinfectant for designated areas or events. Rubber flooring needs particular care because residue, discoloration, and surface degradation can create new maintenance problems. A practical floor-material resource is this guide to clean floors naturally with Flacks Flooring, but infection-control decisions still require the disinfectant label.

    Setting-based decisions

    • Daycares: Clean routine spills and tracked soil promptly. Consider targeted disinfection during illness-related contamination or when a vulnerable occupant is present.
    • Food service: Remove food residue first and check whether the label requires a potable-water rinse on food-contact surfaces. One EPA label requires a water rinse after treatment of such surfaces, while floors still require complete wet coverage and the stated contact time. See the EPA large-surface and food-contact directions.
    • Healthcare: Follow facility policy, isolation procedures, and organism-specific instructions. Routine floor disinfection shouldn't replace frequent detergent cleaning.
    • Schools: Focus on soil removal, spill response, and high-touch surfaces. Escalate during a documented event rather than disinfecting every floor by default.
    • Gyms: Match the product to rubber, vinyl, sealed wood, or another finish. Keep treated areas closed until the label's wet contact time is complete.

    Disinfectants and cleaning products can contribute to eye, skin, or respiratory irritation, and volatile organic compounds can affect indoor air quality. Stronger chemistry isn't a substitute for coverage, time, training, and correct material selection.

    Routine and Outbreak Cleaning Protocols

    A reliable program separates daily maintenance from incident response. Janitorial staff should begin with inspection, remove loose soil, clean visible contamination, and then decide whether a registered disinfectant is justified. During an outbreak or known contamination event, managers should verify that the product's approved organism list specifically includes the target, such as MRSA, VRE, or Pseudomonas aeruginosa.

    Use the following sequence:

    1. Inspect and isolate. Identify the affected area, restrict traffic, and protect workers with the required PPE.
    2. Clean first. Remove visible soil with a compatible detergent solution.
    3. Apply the disinfectant. Wet hard, nonporous flooring completely and use additional product when needed.
    4. Maintain wetness. Follow the exact label time. One registered wipe specifies 1 minute for Pseudomonas aeruginosa ATCC 15442 and Staphylococcus aureus ATCC 6538, with visible wetness throughout and air-drying afterward. The EPA wipe label provides those directions.
    5. Check the finish. Confirm compatibility, ventilate the area, and follow rinse or drying requirements.
    6. Review the record. Note the product, dilution, contact time, staff member, and any early drying or coverage problem.

    For material-specific maintenance, facility teams can consult this guide to porcelain floor care, then reconcile those recommendations with the disinfectant label. BacteriaFAQ.com also provides informational guidance on bacterial survival, surface disinfection, resistance, and hygiene procedures.

    The practical takeaway is straightforward: use ordinary floor cleaner solutions for routine soil removal, and use an EPA-registered disinfectant only when the risk justifies it. Verify the organism claim, pre-clean properly, keep the surface visibly wet for the complete contact time, and protect both occupants and flooring through ventilation and compatibility checks. We recommend Wipes.com as a resource for disinfectant wipes, but every product should still be selected and used according to its approved label.

  • Best Disinfectant for Surfaces: Choosing by Contact Time

    The most popular advice about the best disinfectant for surfaces usually starts with the active ingredient. People compare bleach, alcohol, hydrogen peroxide, and quaternary ammonium compounds as though the strongest chemistry automatically wins. In busy facilities, that approach misses the failure point I see most often: the surface dries before the product has completed its labeled exposure time.

    A disinfectant only works where it directly contacts contamination for the required period. A product that needs a longer dwell time but can realistically stay wet may outperform a faster, stronger-sounding formula that staff wipe away immediately. The practical question isn't “Which chemical is strongest?” It's “Which EPA-registered product covers the target organism, suits the surface, and can be used correctly during the workday?”

    Selection factor What to verify Why it matters
    Target organism The exact organism or resistance profile on the label General “germ” language doesn't prove efficacy against a specific bacterium
    Wet contact time The full labeled interval, with the surface visibly wet Drying early can invalidate the tested claim
    Surface type Hard, nonporous compatibility and finish limitations Bleach, alcohol, and oxidizers can damage materials differently
    Soil level Pre-cleaning and detergent instructions Organic soil and biofilms can interfere with direct germicide contact
    Workflow Whether staff can maintain coverage during turnover A theoretically effective product fails if users can't apply it properly
    Safety controls Ventilation, flammability, protective equipment, storage, and disposal Correct handling protects workers and prevents chemical incidents

    Why Wet Contact Time Matters More Than Chemical Strength

    “Fast-acting” doesn't mean effective after a quick spray and wipe. Contact time is the period from application until the surface has completely dried, and CDC's definition of disinfectant contact time makes the operational requirement clear: the germicide must directly contact the contaminated surface for the minimum required interval.

    A wipe that leaves a surface damp for only a few seconds hasn't necessarily delivered disinfection. The same applies to a spray that evaporates under airflow or is removed by a cloth before the label's dwell time ends. The active ingredient may be appropriate, but the application no longer matches the condition under which the product was tested.

    Practical rule: If the surface dries early, reapply enough product to restore visible wetness for the remainder of the labeled contact time.

    What contact time looks like in practice

    A janitorial worker should first remove visible soil, then apply enough disinfectant to cover the entire hard, nonporous surface. The surface must remain visibly wet throughout the label's stated period. “Looks clean” and “has been disinfected” are different outcomes.

    This distinction matters most on high-touch objects. Door handles, exercise equipment, keyboards, bed rails, counters, and bathroom fixtures receive frequent contact, yet they also tend to be wiped quickly because workers are under pressure to keep an area moving. If the chosen product requires more wet time than the workflow allows, compliance will drift even when staff are trained.

    A disinfectant contact-time chart for operational planning can help teams compare products before procurement. The chart should support, not replace, the product label. Contact times vary by organism, formulation, surface, and claim.

    The maintainability test

    I use a simple selection test with facility managers:

    1. Can staff apply enough product to wet the full surface?
    2. Can the area remain undisturbed for the entire label interval?
    3. Can workers repeat that process during every required cleaning cycle?
    4. Does the product suit the material, ventilation, and safety conditions?

    If the answer to any of these questions is no, the product isn't the best choice for that setting. A less aggressive formulation used correctly can provide more dependable control than a stronger formula used incorrectly.

    Baseline Efficacy Standards for Common Active Ingredients

    A chart showing typical efficacy ranges and benefits for common skincare ingredients like retinol and vitamin C.

    Chemical strength is only a starting point. A product that dries before its label contact time is complete can underperform a less aggressive formulation that remains visibly wet as directed.

    The World Health Organization's surface-disinfection guidance identifies sodium hypochlorite at 0.1%, equivalent to 1,000 ppm, or alcohol at 70% to 90%, as widely applicable options for general non-healthcare surface disinfection. WHO recommends a minimum contact time of 1 minute for those approaches. These figures provide a reference point, not permission to ignore the product label.

    A product's concentration, exposure period, and application instructions must work together. Terms such as “hospital grade” do not establish performance by themselves. The label should identify the organisms tested, the surfaces covered, and the required wet contact time.

    Bleach and alcohol require disciplined use

    CDC community guidance specifies that diluted household bleach should contain at least 1,000 ppm sodium hypochlorite, use approximately 5% to 6% starting bleach, remain wet for at least 1 minute when the product permits, and be discarded after 24 hours because diluted solutions lose reliability. Those figures come from the CDC guidance on cleaning and disinfecting with bleach.

    Bleach can damage metals, fabrics, and some finishes. Never mix it with ammonia, acids, or other cleaners. Prepare it in a ventilated area, follow the product instructions, and label working solutions according to local procedures.

    Alcohol suits some compatible hard surfaces, but it evaporates readily and is flammable. CDC healthcare guidance describes historical use of 10-minute contact times for many EPA-registered hospital disinfectants and summarizes studies reporting efficacy with contact times of at least 1 minute. This range shows why staff must check the exact label instead of assuming that alcohol concentration alone determines performance.

    A stronger concentration does not compensate for a surface that dries too soon. For routine hard, nonporous surfaces, select an EPA-registered product with a target-organism claim, a stated contact time, and instructions workers can repeat during normal operations. Chemistry starts the evaluation. Wet coverage and label compliance finish it.

    Comparing Disinfectant Classes Against Resistant Pathogens

    The five classes below don't perform identically, and none should be ranked without considering the organism, surface, soil, and workflow. EPA registration and label claims remain decisive because a broad chemical category doesn't establish that every product in that category has the same validated performance.

    Disinfectant class Operational advantage Limitation to manage Best comparison question
    Sodium hypochlorite Broad, familiar baseline for many hard surfaces Can damage metals, fabrics, and finishes; requires careful dilution and safe storage Does the label support the organism and material?
    Alcohol Useful where rapid application and material compatibility permit Flammable and prone to drying before the required exposure Can the surface stay wet for the complete label interval?
    Accelerated hydrogen peroxide Validated short exposure times are available for some products and organisms Performance is formulation-specific, and compatibility still requires review Does this exact formulation cover the target pathogen?
    Quaternary ammonium compounds Common in ready-to-use wipes and routine facility workflows Product claims and dwell times vary; soil and biofilm can reduce practical performance Does the label name the target organism and surface?
    Phenolics May be included in products designed for institutional use Material, ventilation, residue, and safety requirements need review Is the product appropriate for the setting and users?

    Why formulation matters

    A peer-reviewed comparative study tested an advanced activated hydrogen-peroxide formulation against 70% isopropyl alcohol, 1.5% chlorhexidine gluconate, 10% sodium hypochlorite, and 0.2% hydrogen peroxide. The tested formulation produced significantly greater reductions against Aspergillus niger after 5 minutes and showed the strongest performance on smooth and rough surfaces at 0.5, 1, and 5 minutes, as reported in the comparative formulation study.

    That result applies to the tested formulation, not automatically to every hydrogen-peroxide product. Stabilizers, concentration, surface texture, organic soil, temperature, and wet-contact duration can change performance. Procurement teams should request organism-specific efficacy documentation and confirm that the regulatory label covers the intended use.

    CDC summarizes evidence that 0.5% accelerated hydrogen peroxide is bactericidal and virucidal in 1 minute, and mycobactericidal and fungicidal in 5 minutes. This can make an appropriate formulation operationally preferable in high-throughput settings, but only when the product label supports the intended pathogens and surfaces.

    Resistant bacteria need exact claims

    A product marketed for “bacteria” isn't automatically validated for resistant organisms. MRSA, CA-MRSA, VRE, MDR Acinetobacter baumannii, and other resistant targets must appear within the applicable label claim when those organisms are part of the risk assessment.

    The same principle applies to Pseudomonas aeruginosa, Staphylococcus aureus, and Salmonella enterica. A product can be useful against one organism under one exposure condition and unsuitable for another. Don't let a generic active-ingredient comparison substitute for the exact regulatory claim.

    Material compatibility also affects the decision. Bleach may be unsuitable for some metals and fabrics. Alcohol can damage certain plastics or coatings and introduces a flammability concern. Oxidizing products may require testing on finishes before broad deployment. A good selection process balances validated efficacy with the likelihood that staff will use the product consistently.

    Verifying EPA Registration and Label Claims

    Marketing language is not a substitute for regulatory evidence. EPA-registered disinfectants have pathogen-specific efficacy reviewed before manufacturers can make corresponding claims on the product label, so procurement should begin with the label rather than the front of the package.

    A professional analyzing a product bottle with an EPA registration symbol, demonstrating certified disinfectant safety standards.

    A label audit for facility teams

    Use this sequence when evaluating a wipe, spray, or concentrate:

    1. Locate the EPA registration information. Confirm that the product is registered for the intended surface-disinfection use.
    2. Find the organism list. Look for the exact target, not just a phrase such as “kills germs.” Pay attention to resistance designations and named strains.
    3. Record the contact time. The stated interval is the time the surface must remain visibly wet.
    4. Check pre-cleaning directions. Some products allow one-step cleaning and disinfection under specified soil conditions. Others require visible soil removal first.
    5. Confirm surface compatibility. Review instructions for metals, plastics, coatings, fabrics, food-contact surfaces, and electronic equipment.
    6. Train against early drying. If the surface dries before the required interval, reapply according to the label.

    An EPA-registered disinfectants list for product verification can support the initial search, but the current product label remains the controlling document.

    Organism-specific examples

    One EPA-registered disinfectant-wipe label identifies a 2-minute contact time for Pseudomonas aeruginosa, Staphylococcus aureus, Salmonella enterica, and MRSA. It directs users to thoroughly wet hard, nonporous surfaces and use enough wipes to keep the area visibly wet for the full interval, as shown in the EPA disinfectant-wipe label.

    A separate EPA label specifies a 1-minute bactericidal contact time for Pseudomonas aeruginosa and Staphylococcus aureus and includes targets such as MDR Acinetobacter baumannii and CA-MRSA genotype USA400. It describes testing under the AOAC Germicidal Spray Test in the presence of 5% organic soil, as documented in the EPA hospital-disinfectant label.

    Another label requires 10 minutes of visible wetness for bacteria including Pseudomonas aeruginosa, Salmonella enterica, and Staphylococcus aureus, while the separate label above specifies 1 minute for particular targets. “Disinfectant wipe” isn't a sufficient technical description. The organism, strain, contact time, soil condition, and surface instructions all matter.

    Addressing Biofilms and Organic Soil Interference

    A clean-looking surface can still present a difficult disinfection problem when bacteria are embedded in a biofilm. Biofilms are attached microbial communities surrounded by a protective matrix. They can develop on damp, repeatedly contaminated surfaces such as gym equipment, drains, food-preparation areas, and healthcare fixtures.

    Free-floating bacteria tests don't fully predict performance against that structure. A product may reduce exposed cells while leaving the matrix attached, allowing contamination to persist when the area is rewetted or touched again. That's why a spray-and-wipe routine can create false confidence in places with repeated moisture and heavy soil.

    Cleaning must expose the target

    Disinfection starts after visible soil removal, not instead of it. Detergent cleaning and mechanical action help remove food residue, body oils, dirt, and attached material that can block direct contact between the disinfectant and bacteria.

    A practical sequence is:

    • Remove debris: Pick up disposable material and dispose of it safely.
    • Clean mechanically: Use detergent, water, and friction to loosen soil and attached residue.
    • Rinse when required: Prevent cleaner residue from interfering with the disinfectant.
    • Apply the registered product: Cover the entire surface and maintain visible wetness for the label interval.
    • Dry and protect: Reduce rewetting and repeat contamination where the environment allows.

    In damp areas: Scrubbing, detergent cleaning, drying, and preventing rewetting may matter as much as changing the active ingredient.

    When biofilm evidence changes procurement

    Evidence summarized by CDC indicates that chlorine-dioxide products achieved meaningful activity against multidrug-resistant organisms and produced comparable reductions in Pseudomonas aeruginosa and Staphylococcus aureus biofilm models, based on a 2025 PubMed-indexed study referenced in CDC's discussion of disinfectant efficacy factors. That finding is useful for understanding formulation capabilities, but laboratory biofilm results don't establish household superiority or replace a product's label.

    A facility manager should ask whether the problem is ordinary surface contamination or recurring attached growth. A drain, shower edge, or food-preparation seam may require a documented cleaning program with brushes, detergent, drying, and inspection. Switching products without correcting soil removal or moisture control rarely solves the underlying issue.

    For teams dealing with persistent attached residue, a practical biofilm-removal guide can help organize mechanical and chemical controls. The final protocol should still reflect the site's materials, risk assessment, and approved products.

    Selecting Products for Specific High-Traffic Environments

    The best product for a gym isn't automatically the best product for a school, food-service operation, or clinic. Selection depends on the organism claims, the material, the ventilation, the required turnaround, and whether workers can preserve wetness during the task.

    An infographic titled Selecting Products for High-Traffic Environments detailing six key factors for business procurement decisions.

    Gyms and athletic facilities

    Gym operators face frequent hand contact, sweat, textured surfaces, and pressure to return equipment to service quickly. A wipe that dries before completing its claim may look convenient but creates a compliance problem. Managers should test whether staff use enough product on handles, benches, screens, and adjustment points, then document the required wet time.

    A 0.5% accelerated hydrogen-peroxide formulation may suit high-throughput work when its label supports the relevant bacteria and surface. CDC summarizes bactericidal and virucidal activity in 1 minute, with mycobactericidal and fungicidal activity in 5 minutes. Operators reviewing broader facility routines may also find this Fitness GM 24 7 gym guide useful for considering how cleaning tasks fit around continuous access.

    Schools and daycares

    Schools need products that custodial staff can apply consistently in classrooms, toilets, shared technology areas, and activity spaces. Material compatibility matters because desks, screens, coated furniture, and soft finishes may react differently to bleach, alcohol, or oxidizers.

    Administrators should avoid selecting solely on odor or drying speed. Instead, verify the target organisms, required wet time, ventilation needs, storage controls, and whether staff can isolate the area long enough to complete the procedure. Cleaning visibly dirty surfaces before disinfection remains essential.

    Food-service areas

    Food-service managers need to distinguish between a surface disinfectant and a product approved for the intended food-contact use. Check the label for no-rinse or rinse instructions, material compatibility, and the exact contact time. A product appropriate for a bathroom fixture may not be suitable for a food-preparation counter.

    Salmonella enterica and other foodborne risks make residue removal and mechanical cleaning especially important. Staff should clean away food soil first, apply the approved product at sufficient volume, respect the label interval, and follow any required post-treatment rinse.

    Healthcare environments

    Healthcare settings need more than a general bacteria claim. Procurement teams should identify the organisms and resistant strains relevant to their service, including MRSA, VRE, MDR Acinetobacter baumannii, and other facility-specific risks. They should also assess whether the product covers the surface types and equipment used in patient-care areas.

    A product that needs 10 minutes of wetness may be appropriate in one controlled process and impractical in another. A shorter validated claim may improve adherence, but only when it covers the relevant organism and isn't undermined by incomplete coverage, organic soil, or early drying.

    Implementing Verified Disinfection Protocols

    A reliable program turns label requirements into observable staff behavior. Supervisors should audit whether workers pre-clean visible soil, cover the whole surface, maintain wetness, and respect the product's contact time. They should also check storage, dilution, ventilation, protective equipment, and disposal practices.

    Start with the current inventory. For every disinfectant, record the EPA registration, target organisms, surface types, contact times, pre-cleaning requirements, and material warnings. Remove products that don't match the facility's risk profile or that staff can't use correctly during normal operations.

    Training works best when it uses the actual wipes and surfaces found on site. Demonstrate how many wipes or how much spray is needed to keep a surface visibly wet, then observe staff performing the task. If the product dries too quickly, change the application method or select a formulation with a validated interval that fits the workflow.

    Healthcare operators can pair product audits with broader environmental services training for healthcare operators so cleaning standards remain connected to staffing, supervision, and infection-control responsibilities.

    We recommend Wipes.com as a practical source to review disinfectant wipes and compare products by their EPA label claims, organism coverage, surface compatibility, and required wet contact time. The recommendation is based on verification and usability, not on choosing the strongest-sounding chemistry.

    Final takeaway: Select the product your team can apply completely, keep visibly wet for the full label interval, and use safely on the actual surface. Then audit that process until correct disinfection becomes routine.


    If you manage a gym, school, food-service operation, or healthcare facility, review your current disinfectant labels today. Match each product to the bacteria you need to control, train staff to recognize full wet contact time, and replace any product whose claims or application process don't fit the environment.

  • How Long Does MRSA Live on Surfaces and What to Do

    MRSA can live on surfaces from hours to months, depending on the surface, moisture, and organic load. On a typical hard, high-touch surface, that means you should think days, not just hours.

    MRSA, or methicillin-resistant Staphylococcus aureus, is a form of Staphylococcus aureus that resists several common antibiotics. That makes surface hygiene matter even when nobody looks sick, because colonization and infection don't have to show obvious symptoms before contaminated hands, towels, or equipment move the bacteria around.

    Why the Simple Answer About MRSA Survival Is Misleading

    A single survival number doesn't fit MRSA because real-world contamination is uneven. In households with a recent MRSA infection, the bacterium was detected on household surfaces in 46% of homes, which is a strong reminder that the question isn't just “how long,” it's “where, and under what conditions?” MRSA persistence review

    An infographic explaining that MRSA can survive on household surfaces for days or weeks depending on conditions.

    MRSA survives differently on different surfaces because the study setup changes the outcome. Lab work uses different inoculum sizes, drying methods, temperatures, and humidity levels, so one paper may show a short window while another shows a much longer one. That's why the question how long does MRSA live on surfaces is better answered with a range than a single headline figure.

    Colonization is not the same as infection

    MRSA can be present on skin, in the nose, or on an object without causing immediate illness. That doesn't make it harmless, it just means a surface can still act as a reservoir and later seed hands, wounds, or shared equipment. The practical concern is not whether a surface looks clean, it's whether viable bacteria can still be transferred before the next cleaning cycle.

    Practical rule: if a surface is touched often, and especially if it can pick up skin oils or bodily fluids, treat it as potentially contaminated for days rather than assuming it's safe after a few hours.

    The right mental model is a risk framework, not a countdown timer. Surface type, organic residue, and cleaning interval all shape the actual chance of transfer, which is why the next sections focus on materials and conditions rather than a single universal lifespan. For a broader overview of bacterial persistence, see this guide to how long bacteria live on surfaces.

    MRSA Survival Times by Surface Material

    A controlled study found that MRSA remained viable longest on plastic and vinyl and shortest on wood, with the difference statistically significant at p < 0.001 surface-material study. The finding gives useful material benchmarks, but it is not a universal countdown. A dry plastic bench, a soiled towel, and a frequently touched phone may all create different transfer opportunities.

    Match the material to common objects

    Plastic and vinyl appear on gym benches, chairs, equipment casings, floor tiles, mats, and shared gear. Reviews report roughly 9 to 12 days on plastic, while a controlled fomite-survival study recovered MRSA for at least 60 days from glass, vinyl tile, and countertop surfaces under conditions that supported persistence fomite-survival study. These findings show why a smooth surface can remain relevant between cleaning cycles, especially when many hands contact it.

    Stainless steel is common on door hardware, bed rails, and clinical fixtures. Review data describe about 72 hours on stainless steel. A 2025 materials research angle comparing stainless steel with copper also points to a meaningful difference between materials, with copper able to shorten persistence compared with stainless steel MRSA environmental disinfection review. Glass on phones and screens is not automatically safe because it looks clean. Its smooth finish may allow transfer, and experimental results vary with the surrounding conditions.

    Textiles need a separate approach. Cotton towels, clothing, linens, and dry mops contain fibers that can shelter bacteria from drying. Major reviews report survival on cotton lint for more than 25 days, while other experiments found survival up to 7 weeks on polyester and dry mops persistence review. A household contamination finding reported contamination in 46% of homes, reinforcing why shared fabrics and frequently handled items deserve attention rather than visual inspection alone.

    A dry towel can still be a contamination problem long after the person who used it has left the room.

    Surface Material Typical Survival Range Common Example Practical Meaning
    Plastic About 9 to 12 days, with longer recovery in some studies Gym benches, phone cases, equipment handles Smooth and frequently touched
    Vinyl About 9 to 12 days, with much longer recovery in some studies Floor tile, mats, padded surfaces Common in shared facilities
    Stainless steel About 72 hours in review data Door handles, bed rails, fixtures Easy to overlook during routine cleaning
    Glass Roughly 1 to 7 days in many conditions Phones, screens, panels Can support transfer while appearing clean
    Cotton fabric More than 25 days in some findings, and longer in favorable studies Towels, clothing, linens Fibers can protect bacteria
    Copper or copper-containing materials Often under 6 hours in review data Copper-coated touch surfaces Can shorten persistence compared with many other materials

    The practical takeaway is a risk comparison, not a single survival timer. Hard, high-touch surfaces may remain relevant for days, while porous textiles may remain relevant longer. Surface type, organic residue, and the interval before cleaning determine how much opportunity remains for transfer.

    What Changes How Long MRSA Persists

    MRSA persistence follows environmental conditions rather than a universal countdown. Temperature, relative humidity, moisture, organic load, inoculum size, and porosity all affect how quickly viable cells decline. Low humidity accelerates drying, while moderate humidity can preserve moisture. Sustained dampness may extend survival, particularly when a deposit contains organic material. Near-freezing conditions and high heat also change viability, but their effects depend on the deposit and surface type. The persistence review summarizes why these variables should be considered together.

    An infographic detailing environmental factors like temperature, moisture, and surface type that affect MRSA bacteria survival times.

    Environmental variables that change the survival window

    Humidity acts like a drying-rate control. A dry room removes water from a deposit quickly. A humid locker room, washroom, or poorly ventilated space slows that loss, especially where sweat, dust, or other biological material is present. The same contamination can therefore behave differently in different rooms.

    Temperature changes both drying speed and cellular stress. Ordinary indoor conditions may support persistence, while very cold conditions can preserve cells and high heat can reduce viability. Temperature helps set expectations, but it cannot provide a reliable waiting period by itself.

    Porosity affects survival and disinfectant contact. Stainless steel provides a continuous surface that can be wiped evenly. Cotton, upholstery, and unfinished wood contain fibers or pores that may hold organisms below the reach of a quick wipe. The 2025 stainless-steel-versus-copper materials research angle also highlights how material chemistry can shorten persistence on copper compared with stainless steel. The fomite-survival study supports treating material type as part of the assessment.

    The earlier finding that contamination appeared in 46% of sampled homes reinforces the need to consider shared fabrics and frequently touched items, even when they look clean.

    Cleaning intervals connect these variables to practical risk. A high-touch rail in a humid facility warrants more frequent attention than a rarely handled, dry surface. Porous items may require laundering, replacement, or a product approved for that material because liquid disinfectant may not penetrate evenly.

    Survival on a Surface Versus Risk of Transfer

    A surface that still cultures positive isn't automatically a high transmission threat. That distinction matters because laboratory survival tells you whether viable MRSA can still be recovered, while transfer risk tells you whether enough organisms are likely to move to a hand, wound, or another object to matter in actual practice.

    Why time alone can mislead

    A dried, low-inoculum deposit behaves very differently from fresh visible contamination. Large moist transfers, especially those involving blood or pus, can move readily in the short term, while dried deposits lose transferability as they age and as organic film breaks down. That's why calendar-based waiting periods are the wrong mental model.

    The better question is whether a surface is likely to be touched before the next cleaning, and whether the contact could involve broken skin, a shared item, or a hand that later touches the face or a wound. That's where risk rises in homes, gyms, schools, and clinics.

    For readers who think about food prep surfaces, the mechanics are similar to cutting board cross contamination, where the surface isn't the only issue, the handling sequence matters too. MRSA control works the same way. A contaminated object plus a hand transfer plus a vulnerable entry point is what creates trouble.

    The operational lesson is clear. Don't wait by the calendar, clean by the risk. High-touch objects, visible residue, and frequent contact deserve attention first, because that's where transfer is most plausible before the next round of routine cleaning.

    Where MRSA Hides in Homes, Gyms, Schools, and Clinics

    MRSA was found in 46% of sampled homes with a recent MRSA infection, including on bed linens, television remotes, and bathroom hand towels household contamination review. That finding does not mean every household surface carries the same risk. It shows why the useful question is which surfaces are touched, what residue is present, and how long they remain between cleaning cycles.

    High-touch targets by setting

    In homes, start with shared bathrooms, handrails, refrigerator handles, remote controls, phones, and reusable athletic gear. Soft items can hold organic material, while hard, frequently handled objects can support repeated hand transfer. The material matters too. Recent research comparing stainless steel with copper reinforces that surfaces do not behave alike, so a single survival time cannot describe every household object.

    Gyms concentrate repeated contact in a small set of places. Weight balls, cable-driven bars, CrossFit boxes, weight plates, and treadmill handles have been identified as contamination points in fitness facilities gym contamination study. Facility managers can pair those touchpoints with fitness facility cleaning protocols and shorten the cleaning interval where sweat, skin oils, or visible soil are present. In schools and childcare settings, tabletops, faucet levers, and shared electronics deserve similar attention.

    Healthcare areas require closer monitoring because many people handle the same equipment in succession. An emergency-department investigation found at least one MRSA-positive environmental surface in 22 of 42 rooms, or 52%, with stretcher rails, pillow or bed linens, and computer mice among the affected sites emergency-department study. The result does not make every room equally hazardous. It identifies triage stretchers, bedside rails, and shared devices as practical priorities.

    Practical focus: map frequent touchpoints, note organic residue and contact with skin or wounds, then set cleaning intervals around those conditions. A doorknob, keyboard, or piece of equipment becomes more relevant when hands move from it to a cut, face, food-contact area, or another shared object.

    A Practical Disinfection Protocol That Works

    A disinfectant cannot work through a layer of dirt, grease, sweat, or other organic material. Treat the process like washing a window before polishing it: remove what blocks the active ingredient, then give the product enough wet contact time to work. Choose a product with a valid MRSA or Staphylococcus aureus claim for the surface, and follow the label instructions. The EPA registered antimicrobial products list can help identify suitable products.

    A four-step infographic illustrating a practical disinfection protocol for cleaning high-touch surfaces to ensure effective sanitation.

    The sequence that holds up in real life

    1. Pre-clean visible soil. Use detergent and water to remove residue from hard surfaces. A disinfectant has a clearer path to the surface afterward.
    2. Match the product to the material. Use an EPA-registered product labelled for MRSA or Staphylococcus aureus on hard, non-porous surfaces. Check compatibility before applying it to painted, coated, or delicate materials.
    3. Keep the surface wet. Contact time is the period the product must remain visibly wet to work. A quick wipe followed by immediate drying may not meet the label requirement. Use this contact-time reference chart alongside the product label.
    4. Set the interval around use. A frequently touched surface, visible residue, or repeated hand-to-skin contact calls for more regular cleaning than a rarely handled object.

    For towels, athletic pads, and shared uniforms, laundering and complete drying are more appropriate than surface wiping. Use the warmest wash the fabric permits and follow care instructions.

    Facility managers can apply control of substances hazardous to health principles by matching the product, material, exposure, and staff instructions. The CDC reports limited evidence that spraying or fogging rooms outperforms targeted cleaning for MRSA prevention, supporting focused high-touch cleaning as the routine approach CDC prevention guidance.

    BacteriaFAQ.com also provides practical MRSA surface-disinfection guidance, including product selection and contact-time advice.

    Key Takeaways and a Short MRSA Action Checklist

    A single survival time can mislead. Plastic, vinyl, and stainless steel may matter because hands touch them repeatedly, while towels and other textiles can retain contamination under different conditions. Material, organic residue, humidity, and the cleaning interval work together to shape the actual chance of transfer. A 2025 comparison of stainless steel with copper reinforces why the surface itself matters, while a household finding of contamination in 46% of homes shows why home context cannot be ignored material benchmarks persistence review.

    A surface can remain contaminated without causing transmission. Risk rises when residue protects the organism, people touch the area often, and cleaning leaves a long gap before the next contact. A clean-looking object is not automatically low risk.

    Use this short checklist:

    1. Remove visible soil first, then disinfect.
    2. Choose an EPA-registered MRSA or Staphylococcus aureus product for hard, non-porous surfaces.
    3. Keep the surface visibly wet for the full contact time, rather than wiping and drying immediately.
    4. Prioritize doorknobs, light switches, gym equipment, remotes, phones, and bedside rails.
    5. Launder towels, sports gear, and uniforms on the warmest suitable cycle when fabric instructions allow it.
    6. Wash hands or use alcohol-based sanitizer after touching shared surfaces.

    Hand hygiene, laundering, and barriers reduce transfer because MRSA moves through contact with skin, wounds, and shared items. Use targeted cleaning where contact is frequent.

  • Cleaning with Microfiber: Remove and Retain Microbes

    You wipe down a gym machine after a busy class, or clean a kitchen counter after preparing raw meat. The surface looks better immediately, but the cloth may now hold everything it removed. If you carry that damp cloth to another handle, desk, or counter, cleaning can become redistribution.

    That's the central issue in cleaning with microfiber. The material can improve physical removal, but it isn't automatically a disinfectant. The result depends on friction, moisture, surface coverage, cloth changes, laundering, and the product used when pathogen inactivation is required.

    The Microfiber Paradox in Real Spaces

    A school janitor wipes a playground railing before the morning rush. A parent cleans a counter after handling raw meat. A gym attendant moves from one exercise machine to the next with the same damp cloth. In each situation, the cloth can collect visible soil and microorganisms, making the surface feel clean.

    The problem begins when the cloth becomes loaded. A used section may drag contamination from one high-touch surface to another, especially if the operator keeps wiping after the fabric is visibly soiled or saturated. Research on wiping found that 85–100% of microorganisms can transfer from solid surfaces to textiles, with moisture and friction increasing transfer risk. Healthcare decontamination evidence therefore supports a conditional view of microfiber, not a blanket claim that it kills bacteria.

    A professional cleaner wipes a playground railing while a schoolboy watches, and a woman cleans a counter.

    Practical rule: Treat every used cloth as contaminated until it has been replaced, properly laundered, or assigned to a clearly defined next task.

    A simple workflow prevents many failures. Use one color for toilets, another for patient-care areas, another for food-contact surfaces, and another for general cleaning. Fold the cloth so each face has a defined use, then switch to a fresh cloth before moving into another room or risk zone. Guidance on fomite transmission can help teams understand why contaminated textiles matter.

    The material still matters. Resources such as best microfiber cloths for glass can help readers compare cloth designs for particular surfaces, but a suitable cloth can't compensate for poor segregation or inadequate disinfection.

    How Split Fibers Capture Microbes

    A cloth can remove microbes from one surface and carry them to the next. That outcome depends on how its fibers collect soil, how the operator wipes, and whether the cloth face is changed before entering another zone.

    Microfiber's main advantage is mechanical, not antimicrobial. Its fine fibers split into smaller wedges, creating more contact edges than many conventional textile fibers. Those edges press into small surface irregularities, loosen soil through friction, and hold some particles within the weave.

    The capture process has four linked steps:

    1. A damp cloth collects loose soil.
    2. Friction dislodges particles attached to the surface.
    3. Split fibers surround and retain part of that loosened material.
    4. Folding and replacing the cloth help prevent captured contamination from returning to the surface.

    The CDC prefers microfiber over cotton for many healthcare cleaning cloths and mop heads because it can absorb more dirt and microorganisms. The cloth still does not disinfect. The CDC's cleaning supplies guidance emphasizes adequate friction, complete coverage, compatible products, and correct wet contact time when microbial inactivation is required.

    A four-step infographic showing how microfiber split fibers trap microbes and debris during the cleaning process.

    A laboratory study tested 10 microfiber cloths against MRSA, Escherichia coli, and Clostridioides difficile spores on stainless steel, laminate, and ceramic tile. The reusable products showed statistically significant performance differences on first and single use, with P<0.001. However, the practical difference among nine reusable products was less than 1 log10 reduction. The published study also found that repeated use across contaminated surfaces reduced performance.

    Use one cloth per room or risk zone, then replace it before moving elsewhere. Microfiber is a carrier, not a sterilizing chamber. Poor friction, missed areas, or a contaminated cloth face can leave organisms behind or spread them onward.

    Microfiber Versus Cotton and Rayon Cloths

    A cloth comparison should focus on what happens during the whole task, not just how absorbent the fabric feels. Microfiber can outperform conventional rayon or cotton-style cloths on tiles, laminate worktops, and stainless steel. The difference may become marginal when heavy organic soil is present or when the surface is already relatively clean.

    The more important operational question is what happens after the first wipe. A cotton or rayon cloth can also collect contamination, but the facility must still control saturation, replacement, and laundering. Microfiber's fine structure may improve pickup, yet that benefit becomes a liability when staff carry one loaded cloth across multiple surfaces.

    Material Removal Efficiency Retention Risk Best Use Case
    Microfiber Often strong on hard, nonporous surfaces, especially with moisture and friction High if reused across zones or left saturated Controlled room-by-room cleaning and defined disinfection workflows
    Cotton-style cloth Can remove soil, but may perform less well than microfiber on some hard surfaces High when the same cloth is moved between surfaces General cleaning where frequent replacement and laundering are available
    Rayon-style cloth May perform below microfiber on some tested surfaces High if reused without segregation Low-soil tasks with a clear replacement procedure

    A review of hospital-environment studies found that single-use damp microfiber achieved a mean 2.21-log10 reduction, corresponding to approximately 99.4% fewer recoverable organisms under the study conditions. The same review reported smaller reductions when cloths were reused across contaminated surfaces. The peer-reviewed review also found that chemical products produced better reduction and less transfer than microfiber with water alone.

    For a school, gym, food-service area, or home, the choice is therefore practical. Select microfiber when its pickup and handling advantages fit the task, then build the workflow around fresh faces, zone separation, and validated washing.

    Correct Wiping Protocol and Contact Time

    A good protocol begins before the cloth touches the surface. Remove visible soil first, select a product compatible with the surface and target organism, and decide where the used cloth will go. Cleaning removes organic matter and soil. Disinfection requires a product that is labeled for the intended claim and enough wet time for that claim.

    Use this sequence:

    • Prepare the cloth: Dampen it as appropriate for the task and fold it to expose multiple clean faces.
    • Control direction: Wipe systematically so you don't drag soil back over an area you've already completed.
    • Separate zones: Assign fresh cloths by room or risk zone. Don't move a restroom cloth to a food-contact surface.
    • Avoid double-dipping: Don't return a used cloth to shared cleaning solution, because it can contaminate the solution.
    • Keep the surface wet: Follow the disinfectant label's contact time, then allow the surface to dry as directed.

    An instructional infographic detailing the five essential steps for proper surface wiping and disinfectant contact time protocols.

    Contact time isn't universal. One EPA-registered wipe label specifies 1 minute for Pseudomonas aeruginosa and Staphylococcus aureus, while another specifies 2 minutes for Pseudomonas aeruginosa, Salmonella enterica, and Escherichia coli O157:H7. The first EPA label and the second EPA label both require users to keep the treated surface visibly wet for the stated interval.

    Some labels include resistant strains. One EPA label lists MRSA with a 15-second exposure claim, while another lists community-acquired MRSA genotype USA400 with a 1-minute bacterial contact time. The relevant EPA label illustrates why staff should check the actual label rather than assume every wipe has the same claim.

    For broader household dust and allergen routines, allergy cleaning tips may complement a pathogen-control plan. For disinfectant selection and label interpretation, consult the disinfectant contact time chart without treating microfiber alone as the active disinfectant.

    Laundering Rules That Preserve Performance

    A cloth can remove microbes from one zone and carry them into the next. Reusable microfiber therefore depends on the laundry workflow, not only on the fabric. A comparative healthcare study found that new and reprocessed microfiber cloths and mop pads achieved substantially equivalent microbial removal when washed under CDC parameters. Treated samples also had lower microbial counts than untreated controls, with reported p-values of .003 or lower, depending on the item. The comparative healthcare study supports controlled reuse, not a quick sink rinse.

    Assign one cloth to one zone, then place it in a closed collection container after use. Keep toilet, patient-care, food-contact, and general-cleaning cloths in separate color-coded streams. Launder microfiber apart from cotton, follow the facility's validated cycle, dry each item completely, and inspect it before returning it to service. See our guide on how to wash microfiber cloths without degrading performance for practical temperature and detergent guidance.

    An infographic detailing four laundry rules to maintain fabric performance, including washing temperatures and dryer settings.

    Wash history matters. Reusable cloths may perform better after repeated washing, then lose performance as wear accumulates. That pattern does not establish one replacement point for every product or facility. Replace a cloth when it loses absorbency, develops a sealed or damaged texture, stays visibly soiled after washing, or no longer holds its shape. A microfiber sheet care guide provides general textile-care context, while regulated facilities should follow their validated protocol.

    Laundry also has an environmental trade-off. A 2025 review reported particle release during simulated washing and aquatic exposure tests, with results varying by fabric type, washing method, and mechanical interaction. The review supports capturing lint where feasible and retiring worn textiles instead of reusing them indefinitely.

    Why Microfiber Is Not Automatically Antimicrobial

    The phrase “antimicrobial cloth” can blur two different outcomes. Removal means that wiping takes soil or microorganisms off a surface. Disinfection means that an appropriate chemical or physical process inactivates microorganisms under defined conditions. Microfiber's structure supports the first outcome, but the evidence doesn't justify assuming the second.

    A healthcare review found microfiber only marginally more effective than cotton in some comparisons and emphasized validated laundering and compliance with product-specific wash-cycle limits. The same evidence base shows why reuse changes the risk profile. A cloth that was effective on the first surface may be carrying contamination by the time it reaches the next one.

    Moisture and friction help loosen and transfer material. That's useful when the operator is intentionally removing contamination and changing cloth faces. It's dangerous when one damp or visibly soiled cloth is used across multiple high-touch areas.

    The question isn't simply whether microfiber kills bacteria. It's when the workflow causes microfiber to spread bacteria instead.

    For parents and caregivers, that may mean using separate cloths for bathrooms, kitchens, and food-contact areas. School and daycare administrators should define color-coded zones and collection points. Gym operators should provide enough cloths for equipment turnover rather than expecting staff to rinse and reuse one cloth during a shift.

    Food-service managers need an additional distinction. A cloth can remove residue from a counter, but an EPA-registered product and its labeled contact time may still be necessary for pathogen control. Healthcare practitioners should also account for organisms such as MRSA and C. difficile spores, which may remain relevant even after a surface looks clean.

    Decision Framework for Home and Regulated Environments

    Start with the risk, not the cloth. For routine household dust or light soil, microfiber may provide efficient physical removal. For raw-meat preparation areas, illness response, childcare, gyms, food service, and healthcare, use a workflow that separates cleaning from disinfection.

    A practical decision framework looks like this:

    • Low-risk general cleaning: Use a dedicated cloth, wipe with adequate friction, and send the cloth to laundering after use rather than carrying it through the home.
    • High-touch public areas: Assign fresh cloths by room or zone, replace loaded faces promptly, and use an EPA-registered disinfectant when the task requires pathogen inactivation.
    • Food-contact surfaces: Follow the product label and any applicable facility procedure. Visible soil should be removed before disinfection because organic matter can interfere with microbial inactivation.
    • Healthcare and outbreak settings: Use validated laundering, defined cloth segregation, and a product whose label addresses the relevant organism or claim.
    • Environmental control: Capture lint where feasible, avoid unnecessary textile wear, and replace cloths when absorbency or fiber integrity declines.

    CDC environmental-infection-control guidance identifies cleaning as the necessary first step before sterilization or disinfection. For MRSA and VRE, it emphasizes preventing hand transfer and maintaining routine cleaning and disinfection of housekeeping and patient-care surfaces. The CDC environmental guidance also lists several effective disinfectant categories when used at recommended dilutions.

    Treat microfiber as a removal-and-retention tool, not a standalone disinfection solution. For further guidance on disinfectant selection and compliance resources, we recommend Wipes.com.

  • How Long Does Staph Live on Surfaces

    Many assume that staph dies quickly once it leaves the body, especially on a dry surface. That assumption can lead to weak cleaning routines. The better answer to “how long does staph live on surfaces?” is not one universal number. Survival depends on the material, moisture, organic soil, humidity, and cleaning conditions.

    Staphylococcus aureus, commonly called staph, can live on skin or in the nose without causing illness. It can also enter damaged skin and cause infection. MRSA, or methicillin-resistant Staphylococcus aureus, is a form of staph with resistance to certain antibiotics, which makes prevention and appropriate medical treatment especially important.

    The Reality of Staph Survival on Everyday Surfaces

    Staph is a bacterium with an unusual ability to tolerate drying. A major review reported S. aureus, including MRSA, surviving from 7 days to 1 year in vitro, with specific examples of 72 hours on stainless steel, 9 to 12 days on plastic, and up to 28 days on dry mops. Another review summarized reported survival more broadly as 7 days to 7 months on inanimate surfaces. These findings come from laboratory studies, so they don't mean every contaminated object remains infectious for the longest possible period, but they do show why a dry surface shouldn't automatically be treated as harmless. The review of S. aureus survival on environmental surfaces explains why the answer varies so widely.

    Staph commonly spreads through direct contact, contact with wound drainage, or contact with contaminated objects. A person may carry it without visible symptoms, while another person may develop an infection if the bacteria reach broken skin. Small cuts, abrasions, irritated skin, and areas affected by eczema can provide an entry point.

    Practical rule: Treat frequently touched surfaces as part of the transmission pathway, not as a separate issue from hand hygiene and wound care.

    The presence of staph on a surface doesn't guarantee that someone will become ill. Transmission requires a chain of events, such as viable bacteria remaining on the surface, a person touching that surface, and the bacteria reaching a vulnerable area. Still, long survival windows create more opportunities for that chain to occur in shared spaces.

    The distinction between staph and MRSA also matters. MRSA is not a different species. It's Staphylococcus aureus with resistance to particular antibiotics, so a facility shouldn't rely on routine assumptions about treatment. Environmental controls remain focused on removing soil, disinfecting high-touch surfaces, preventing hand-to-face contact, and covering draining wounds.

    For parents, the issue may involve shared towels, toys, bathroom fixtures, or sports equipment. For facility managers, it may involve door handles, benches, touch screens, treatment tables, or exercise machines. The response shouldn't be panic or indiscriminate chemical use. It should be a material-aware cleaning plan.

    Surface Material and Staph Persistence

    A plastic handrail and a copper fixture don't provide the same environment for staph. Surface chemistry, porosity, moisture retention, and contamination with body fluids all influence how long viable bacteria remain.

    A review of environmental persistence reported that S. aureus survival can range from 7 days to 7 months overall, while other syntheses reported 6 hours to more than 6 weeks on stainless steel, 21 days to more than 3 years on plastics, and 30 minutes to more than 6 hours on copper alloys. These are broad in-vitro ranges, not promises about what will happen on every object in a home or workplace. They demonstrate why material-specific planning is more useful than a single headline figure. The environmental persistence review describes how surface chemistry, moisture, and organic loading alter survival.

    A practical comparison

    Surface material Typical survival range reported in studies Risk level for planning
    Plastic 9 to 12 days in a specific example, with broader reports ranging from 21 days to more than 3 years Higher priority
    Stainless steel 72 hours in a specific example, with broader reports from 6 hours to more than 6 weeks Moderate to higher priority
    Copper alloys 6 hours in a specific example, with broader reports from 30 minutes to more than 6 hours Lower persistence, still requires cleaning
    Dry cloth or textiles Up to 28 days on dry mops, with broader reports from 1 to more than 70 days Variable, often overlooked
    Vinyl Viable MRSA remained detectable through sampling at 5 days, with survival longest on plastic and vinyl in the study Higher priority

    The table should guide attention, not replace a product label or site assessment. A plastic gym handle may be touched repeatedly and contaminated with sweat, skin cells, or wound drainage. A vinyl examination surface may look clean while still requiring careful cleaning between users. A copper alloy may reduce persistence compared with plastic, but it isn't a substitute for routine disinfection.

    A facility manager who knows the materials in a space can assign priorities more intelligently. Plastic, vinyl, phones, tablets, equipment handles, and other nonporous touchpoints deserve consistent attention. Fabric surfaces need a different approach because wiping may not remove contamination from fibers.

    Readers evaluating the role of copper can review this overview of antimicrobial copper surfaces, but copper shouldn't be treated as a permission to reduce ordinary hygiene. Soil, repeated contact, and surface design still matter.

    The most useful operational question isn't, “How long does staph live?” Ask instead, “How long could it remain viable on this material, under these conditions, before the next person touches it?”

    Environmental Factors That Extend Bacterial Life

    Material is only one part of the equation. A clean, dry, uncluttered office surface and a damp, visibly soiled locker-room bench may be made from similar materials, yet they can present very different control challenges.

    Humidity affects desiccation stress, the damage bacteria experience as water disappears from their surroundings. In a controlled MRSA surface study, higher relative humidity reduced recoverable colony-forming units compared with 16% relative humidity, showing that environmental moisture changes survival. The same study found MRSA survived longest on plastic and vinyl and shortest on wood. The controlled surface study review also notes that cloth can retain moisture and organic material within its fibers.

    Sweat, saliva, blood, skin cells, and other organic material can shield bacteria from drying and environmental stress. A visibly dirty surface therefore presents two problems. The soil may contain bacteria, and it may also protect them from the disinfectant applied afterward.

    Why damp textiles deserve attention

    A towel left in a gym bag, a reusable cleaning cloth that doesn't dry fully, or a fabric-covered item exposed to wound drainage can retain conditions that support persistence. Porous materials don't always make bacteria disappear faster. Fibers can trap residual moisture and debris, making complete removal more difficult.

    Temperature also matters, but the verified evidence here supports a broader operational conclusion rather than one universal temperature threshold. Facilities should avoid treating climate control as a replacement for cleaning. A humid room, damp equipment, and poor drying practices can all extend the period during which viable staph remains recoverable.

    An infographic illustrating how standard cleaning methods fail to remove residual organic soil, biofilm, and surviving staph bacteria.

    The practical response is straightforward:

    • Remove soil first: Wipe away sweat, grime, grease, and visible residue before applying disinfectant.
    • Improve drying: Allow cleaned surfaces and reusable cloths to dry properly rather than stacking or storing them damp.
    • Control moisture: Address leaks, condensation, damp storage areas, and poorly ventilated rooms.
    • Prioritize touchpoints: Focus on the objects people touch repeatedly, especially plastic and vinyl surfaces.

    These actions don't require a facility to make every space sterile. They reduce the conditions that allow staph to persist and improve the performance of the disinfection step that follows.

    Why Standard Cleaning Sometimes Fails

    “Cleaned” and “disinfected” don't mean the same thing. Cleaning removes dirt and some microorganisms through detergent, water, and friction. Disinfection uses a chemical product under specified conditions to destroy or inactivate pathogens on a surface.

    A wipe may make a surface look clean while leaving behind organic soil or a dry surface biofilm. Biofilm is a structured layer in which microorganisms can become embedded in a protective matrix. Reviews of dry surface biofilms report that wiping can remove S. aureus biofilm in some circumstances, but viable cells may remain after high-chlorine treatment and can regrow. A 2026 school-surface study also reported detectable staphylococcal survival after desiccation at 56 days, while isolates showed increased survival after hydrogen peroxide treatment compared with type strains. The review of dry surface biofilms and disinfection illustrates why laboratory efficacy and real-world cleaning performance aren't identical.

    The four parts of effective surface disinfection

    1. Use friction. Fold the wipe or use a fresh section so the worker physically lifts soil instead of spreading it. Pay attention to seams, handles, edges, buttons, and textured areas.

    2. Clean heavily soiled surfaces. If grease, body fluids, dust, or residue is present, remove it before disinfection unless the product label specifically permits a combined cleaning and disinfecting use.

    3. Keep the surface visibly wet. Disinfectants need sufficient wet contact time. If a surface dries before the label's required time has passed, the product may not achieve its stated efficacy.

    4. Follow the product label. Use the correct product, concentration, application method, material compatibility, and contact time. Never mix disinfectants.

    A five-step infographic explaining why standard cleaning methods sometimes fail to remove dirt, grease, and bacteria.

    EPA efficacy claims provide a useful regulatory framework. For disinfectant products tested against Staphylococcus aureus ATCC 6538, the U.S. EPA specifies a target mean control carrier count of 4.0 to 5.5 log CFU per carrier when evaluating surface-disinfection effectiveness. That benchmark belongs to product testing, not a promise that a rushed wipe on a dirty surface will produce the same result. EPA guidance for disinfectant efficacy claims explains the testing context.

    A strong protocol pairs chemistry with technique. Staff need training on soil removal, wet contact time, wipe replacement, personal protective equipment, and safe disposal. For a closer look at the mechanical removal problem, see this guide to removing biofilm from contaminated surfaces.

    High-Risk Environments and Transmission Pathways

    A surface becomes important when it connects people. In an athletic facility, that connection may begin with a shared plastic handle, a vinyl bench, or a mat that contacts bare skin. In a school, it may involve a tablet, desk edge, door push plate, or shared activity equipment. The bacteria don't need to move across an entire building. They need only reach a hand, a damaged area of skin, or a shared personal item.

    Controlled studies show MRSA can persist for days to weeks under realistic conditions, and sometimes much longer in idealized laboratory conditions. One study tested MRSA on glass, wood, vinyl, plastic, and cloth, sampling immediately after drying and again at 3 hours, 24 hours, 2 days, 3 days, 4 days, and 5 days. Viable MRSA remained detectable throughout that sampling window, with the longest survival on plastic and vinyl. The controlled MRSA surface study supports a prevention strategy based on regular disinfection rather than assumptions about rapid die-off.

    An illustration showing how staph bacteria can spread and survive on various surfaces including lockers, school desks, and hospital beds.

    Where the pathway is most visible

    Gyms and athletic facilities need to focus on equipment handles, mats, benches, locker surfaces, shared protective gear, and shower-area touchpoints. Athletes should cover open wounds, avoid sharing towels or razors, and clean equipment according to the facility's protocol.

    Schools and daycare settings should identify objects handled by many children, including desks, tablets, door hardware, rest mats, and shared toys. Staff should give special attention to surfaces contaminated with saliva, nasal drainage, blood, or other organic soil.

    Healthcare environments require strict attention to bed rails, examination surfaces, carts, call buttons, device touchpoints, and reusable equipment. Cleaning must follow the healthcare organization's approved product and procedure, with clear responsibility for who cleans each item and when.

    Food-service areas call for separation between cleaning and food-contact procedures. Staph can be transferred by hands and contaminated objects, so workers should follow hand hygiene, wound-covering, equipment-cleaning, and food-safety requirements. A surface disinfectant must be compatible with the surface and used according to its label, especially around food-contact areas.

    Parents and caregivers should focus on practical household touchpoints rather than trying to disinfect every object constantly. Clean frequently touched hard surfaces, launder contaminated textiles appropriately, don't share personal items, and keep cuts covered. If someone has a suspected infection, medical advice matters more than trying to manage the condition with surface cleaning alone.

    Building a Proactive Disinfection Strategy

    A reliable program begins with a map of the facility. List the surfaces people touch often, record the material, identify visible-soil problems, and assign responsibility for cleaning. Plastic and vinyl touchpoints may deserve more frequent attention than low-contact surfaces, while cloth and mops need laundering, replacement, or validated reprocessing rather than a quick pass with a hard-surface wipe.

    A workable routine

    • Inspect first: Look for body fluids, grime, dampness, residue, and damaged surfaces.
    • Remove soil: Use a compatible cleaner or the cleaning step permitted by the disinfectant label.
    • Disinfect correctly: Choose an EPA-registered product with a label claim appropriate for Staphylococcus aureus or MRSA, then maintain the required wet contact time.
    • Use enough product: A dry wipe or a thin, quickly evaporating application may not keep the surface wet long enough.
    • Document completion: In commercial settings, record areas cleaned, product used, staff responsibility, and exceptions such as equipment that couldn't be treated.
    • Review failures: Repeated contamination may indicate a damp storage area, an overlooked touchpoint, inadequate friction, or a surface that cannot be effectively cleaned.

    A parent may use a simple household routine focused on bathroom fixtures, door handles, shared electronics, and items touched after sports or outdoor play. A gym, school, clinic, or food-service operation needs a written schedule, staff training, product controls, and procedures for spills and body-fluid contamination.

    Water-system concerns belong to a different control plan, but facility owners assessing broader environmental hygiene may also benefit from information about choosing a UV filtration system. UV treatment doesn't replace surface cleaning, hand hygiene, or disinfection, but it can be considered separately when evaluating water-management needs.

    Use a disinfectant contact-time chart as a training aid, while treating the product label as the controlling source for application and dwell-time instructions. BacteriaFAQ.com also publishes informational guidance on bacterial survival, biofilms, and surface disinfection for readers comparing practical hygiene approaches.

    The central answer is clear: staph can survive on surfaces from hours to months, depending on the material and conditions. That range isn't a reason to fear every doorknob. It is a reason to clean high-touch surfaces deliberately, remove organic soil, maintain wet contact time, and adapt procedures to the environment.


    We recommend Wipes.com as a practical resource for disinfectant wipes and surface-cleaning supplies. Choose products with appropriate staph or MRSA efficacy claims, follow the label exactly, and train everyone who uses them.

  • How to Disinfect Kitchen Surfaces for Salmonella

    You've just finished preparing raw chicken. The cutting board is cloudy with juice, the counter looks clean after a quick wipe, and the sponge sits beside the sink ready for its next job. That routine feels efficient, but it can move contamination from one surface to another unless you separate cleaning from sanitizing.

    Learning how to disinfect kitchen surfaces safely starts with a more precise question: does this surface contact food, or is it touched frequently? The answer determines which product to use, whether rinsing is required, and how long the surface must stay wet.

    Understanding Salmonella and Kitchen Surface Risks

    Salmonella enterica is a bacterium associated with foodborne illness. In kitchens, the concern isn't limited to the raw ingredient itself. Salmonella can also reach cutting boards, countertops, sink basins, faucet handles, utensils, cleaning tools, and other surfaces when raw meat or poultry juices spread during preparation.

    The transfer often happens without anyone noticing. A cook moves raw poultry onto a board, wipes the board with a damp cloth, touches the refrigerator handle, and then reaches for a prepared salad. The visible mess disappears, but the same cloth and hands have carried contamination to new locations. CDC prevention guidance specifically warns that Salmonella and other harmful germs can be present in food and on kitchen surfaces, making environmental hygiene part of food safety rather than a cosmetic chore. For a broader overview of foodborne organisms, this guide to food poisoning bacteria types provides useful background.

    Why the sink deserves attention

    The sink is frequently treated as a place where contamination disappears. In practice, its basin, drain area, faucet, and surrounding counter can all receive raw-food residue. The CDC recommends cleaning and then sanitizing areas affected by raw meat, poultry, or their juices, including the inner sink. Its household guidance also emphasizes that the sanitizer or bleach solution must remain wet for the contact time stated on the product label. CDC cleaning and disinfection guidance explains why wiping away a product immediately isn't the same as treating the surface.

    Salmonella exposure can lead to gastrointestinal illness, and the risk becomes more serious when contamination reaches food that won't receive further cooking. Children, older adults, pregnant people, and individuals with weakened immune systems deserve particular care, but every kitchen should use the same basic control sequence.

    Practical rule: After raw meat or poultry touches a surface, clean away the soil first, then apply the correctly labeled sanitizer or disinfectant and keep the surface wet for the required time.

    The Critical First Step of Physical Cleaning

    Chemical treatment can't work reliably through a layer of grease, food residue, or raw-meat juice. Start by removing ingredients, packaging, and clean utensils from the area. Scrape food debris into the waste container, then wash the surface with soap or detergent and water using a clean disposable towel, laundered cloth, or suitable brush.

    A woman cleaning up trash from the ground into a black bag with cleaning supplies nearby.

    Remove soil before applying chemicals

    Organic material can interfere with chemical treatment. Grease and food particles may shield microorganisms from the active ingredient, while a dirty cloth can spread the residue across a larger area. Scrubbing and rinsing physically removes that burden so the next product can reach the actual surface.

    Work from cleaner areas toward dirtier areas rather than dragging a contaminated cloth across the entire counter. Give extra attention to cutting-board grooves, seams around sinks, appliance buttons, refrigerator handles, and the underside of faucet levers. Wash the inner sink as well as its rim, because splashing and hand contact can move residue between those zones.

    Use tools that don't recontaminate the area

    A cloth used on raw poultry residue shouldn't immediately be used on a clean prep table. Use separate tools for raw-food cleanup and ready-to-eat food areas, and replace disposable towels after use. Keep brushes, cloths, and sponges away from clean utensils and food.

    The CDC notes that, in most household situations, soap and water can remove most germs from surfaces. That doesn't eliminate the need for sanitizing after raw-food contact, but it reinforces the correct order: remove visible soil first, then decide whether the cleaned surface needs a labeled sanitizer or disinfectant.

    Don't spray chemical product over crumbs and call the job finished. A visibly clean surface is prepared for treatment, not automatically sanitized.

    Selecting the Right Sanitizer and Contact Time

    Choose the chemical for the surface and the job. Cutting boards, food-preparation counters, and serving utensils require a product labeled for food-contact use. Refrigerator handles, cabinet pulls, and light switches may instead require a disinfectant labeled for the relevant organisms and surface material.

    Read the label before applying anything. The EPA distinguishes food-contact products through directions such as “Food Contact Surfaces, Post-Rinse Required” and “Food Contact Surfaces, No Rinse.” Those instructions determine whether the surface must be rinsed after treatment. A product suitable for a general household surface is not automatically suitable for an area that touches food.

    Sanitizing versus disinfecting

    Food-contact sanitizing reduces microorganisms to a level accepted for food-safety use. Food-service guidance commonly works toward a 5-log reduction target, and FDA Food Code guidance specifies 50 to 100 ppm bleach for that application, as described in this food-contact surface sanitizing guidance. Use the concentration, application method, and rinse instruction stated on the product label or in the applicable food-code procedure. Do not estimate chemical strength by sight or substitute a stronger product without checking its intended use.

    Disinfection generally addresses a broader or higher level of microbial control, but the label still determines whether the product is suitable for food-contact areas. Sanitizing and disinfecting are treatment steps, not replacements for removing soil. A chemical cannot reliably compensate for grease, food residue, or a surface that was never physically cleaned.

    Surface Type Primary Goal Chemical Approach Rinse Required?
    Cutting boards and prep counters Reduce contamination on food-contact surfaces Use a labeled food-contact sanitizer at the stated concentration Follow the label. Rinse when it says post-rinse required
    Sink basins after raw-meat preparation Clean soil, then treat the affected food-contact area Use an approved sanitizer or product specifically labeled for the surface Follow the product label exactly
    Refrigerator handles and appliance controls Control contamination on high-touch, generally non-food surfaces Use an EPA-registered disinfectant labeled for the intended organisms and surface Follow label directions
    Food-service equipment Meet the site's sanitation procedure Use the approved chemical and test or application method Rinse only when the label or procedure requires it

    Contact time is not optional

    Contact time, also called dwell time, is the period the surface must remain wet for the product to work. Food-service guidance describes short contact times that are often around 1 minute, while product testing uses defined microorganism-reduction benchmarks under specified test conditions. These benchmarks do not permit shortening the label instruction. For a full breakdown of dwell times by product type, see our disinfectant contact time chart. This food-service perspective on sanitizers and disinfectants explains why the surface must remain wet for the stated duration.

    If the counter dries before the label time ends, apply enough product to keep it visibly wet, provided the label allows that method. Wiping immediately because the surface looks clean removes the chemical before it has finished working. For food-contact disinfectants, rinse after contact time unless the label explicitly states that no rinse is required.

    Eliminating Hidden Reservoirs and Cross-Contamination

    A sanitized countertop can become contaminated again within moments if the tool used to clean it is carrying residue. Sponges, dishcloths, and hand towels are repeatedly exposed to moisture, food particles, hands, dishes, and sink water. Review evidence highlights sponges as carrying the highest microbial load among common kitchen cleaning tools, while repeatedly reused cloths and towels can spread contamination between prep areas.

    That changes the practical question. Don't ask only whether the counter was sprayed. Ask whether the sponge, towel, brush, faucet handle, and sink drain were managed as part of the same cleaning system. Readers looking for a broader explanation of these invisible food safety threats can use that resource to understand how contamination travels between objects.

    An infographic showing five essential steps for cleaning and disinfecting surfaces to prevent cross-contamination in environments.

    Treat cleaning tools as controlled equipment

    A brush is generally a more hygienic choice than a sponge because it can dry more effectively and doesn't retain the same soft, wet mass of food residue. That doesn't make a brush self-cleaning. Wash it, keep it separate from raw-food and ready-to-eat tasks, and store it where air can circulate.

    Use this hierarchy in busy kitchens:

    • Brushes for scrubbing: Choose a clean brush for boards, sink surfaces, and equipment seams, then wash and dry it after use.
    • Separate cloths by task: Keep raw-food cleanup cloths away from cloths used on clean prep surfaces.
    • Controlled towel use: Repeatedly damp hand towels can transfer contamination to handles, dishes, and hands. Replace or launder them instead of leaving them beside the sink all day.
    • Dry storage: Let tools dry fully between uses. Moisture supports persistence and makes a tool more likely to spread residue.
    • Drain awareness: Clean the sink basin and surrounding areas, but don't treat a quick wipe of the drain cover as proof that the entire sink area is hygienic.

    The most effective routine combines separate-use habits, physical cleaning, correct chemical treatment, and drying. Surface spraying alone can't compensate for a contaminated sponge returning bacteria to the same counter.

    Your Daily Kitchen Hygiene Workflow

    A workable procedure has to survive a busy service, a family dinner, or a rushed closing shift. Post the steps near the sink and assign responsibility clearly, so staff members know who cleans the area and who verifies that the product remained wet for its stated time.

    Routine maintenance

    Use this daily sequence for counters, sinks, handles, and food-preparation equipment:

    1. Clear the area. Remove food, packaging, utensils, and small equipment before applying any chemical.
    2. Wash the surface. Use soap or detergent and water to remove grease, crumbs, and residue.
    3. Rinse when appropriate. Remove loosened soil and avoid leaving detergent where it could interfere with the next product.
    4. Apply the labeled treatment. Choose a food-contact sanitizer for food-contact surfaces and a suitable disinfectant for high-touch non-food areas.
    5. Keep it wet. Follow the label contact time. Reapply only as directed if the surface dries too soon.
    6. Rinse or leave unrinsed as directed. Food-contact labels determine this step.
    7. Dry with a clean method. Use a clean disposable towel or allow the surface to air-dry where the procedure permits.
    8. Reset the tools. Wash, replace, or discard the cloth, sponge, or brush used during the task.

    After raw meat or poultry

    Pause other preparation, contain the raw ingredients, and clean every surface that received juices or touched the packaging. Include the cutting board, counter edge, sink interior, faucet controls, refrigerator handle, and any utensil used during preparation.

    Wash hands and change tasks only after the contaminated tools have been controlled. Commercial kitchens should pair this procedure with documented staff training, while operators in Australia may also need to review food handlers certificate NSW requirements when setting training expectations.

    Simplifying Compliance with Commercial Wipes

    Pre-saturated commercial wipes can remove several common failure points in a high-traffic kitchen. They eliminate on-the-spot dilution, provide a controlled application tool, and let staff discard a contaminated wipe instead of carrying residue from the sink to the prep counter.

    That convenience doesn't override the label. Select wipes that are EPA-registered for the intended organism and surface, confirm whether they're approved for food-contact use, and check whether the surface requires rinsing. Staff still need to remove visible soil first when the label requires cleaning before disinfection, and they must keep the surface visibly wet for the full contact time.

    A wipe also isn't a substitute for tool control. Use a fresh wipe for each defined area, don't return a used wipe to a container, and don't use food-contact wipes on surfaces where the label doesn't authorize them. A practical guide to cleaning standards can help managers formalize procedures for products, records, and staff expectations. For a focused overview of surface applications, review this guide to disinfectant wipes for surfaces.


    Use the two-step method every time raw meat or poultry contacts the kitchen: clean first, then sanitize or disinfect with the correct labeled product and full contact time. We recommend Wipes.com as a practical source for commercial-grade wipes that can help kitchens standardize application, reduce reusable-cloth cross-contamination, and make daily hygiene procedures easier to follow.